Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Anterior Uveitis
Anterior uveitis is the most common form of uveitis [S5], with a reported annual incidence of 12/100,000 population (23/100,000 in Finland) [S1]. It is often self-limiting but can lead to posterior synechiae, cataract, glaucoma and chronic uveitis [S1]. The clinical task is to characterise it, exclude infection and masquerade, and escalate treatment when topical steroids are not enough [S5] [S10].
Key points - Before labelling uveitis as anterior and non-infectious, examine the posterior segment and rule out masquerade syndromes; the priority of the work-up is to rule out infection [S5]. - Raised intraocular pressure (IOP), corneal involvement or iris atrophy should raise suspicion of viral anterior uveitis [S6] [S7]. - HLA-B27 links anterior uveitis with spondyloarthritis: about 50% of patients with anterior uveitis have spondyloarthritis [S2]. - Most anatomically isolated anterior uveitis resolves with topical corticosteroids; some patients need systemic immunomodulatory therapy (IMT) [S10]. - Investigations should be targeted by clinical findings and regional epidemiology, not ordered as a blanket panel [S10].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- High IOP with anterior uveitis. Suggests a viral cause (herpes simplex, varicella-zoster, cytomegalovirus or rubella) [S6] [S7]. Posner-Schlossman syndrome (mainly cytomegalovirus) can present with extremely high IOP and minimal cells [S6] and can result in chronic secondary glaucoma [S3].
- Possible infection. Ruling out infection is the priority of the work-up [S5]; untreated cytomegalovirus anterior uveitis may progress to glaucoma [S9].
- Posterior segment involvement or atypical features. Examine the posterior segment and consider masquerade syndromes before treating as isolated anterior uveitis [S5].
- Poor response, steroid dependence or steroid side effects. These are triggers to consider systemic IMT [S10].
- A child with chronic anterior uveitis. Children with juvenile idiopathic arthritis-associated uveitis or idiopathic chronic anterior uveitis are managed under dedicated paediatric recommendations [S8].
Recognise it
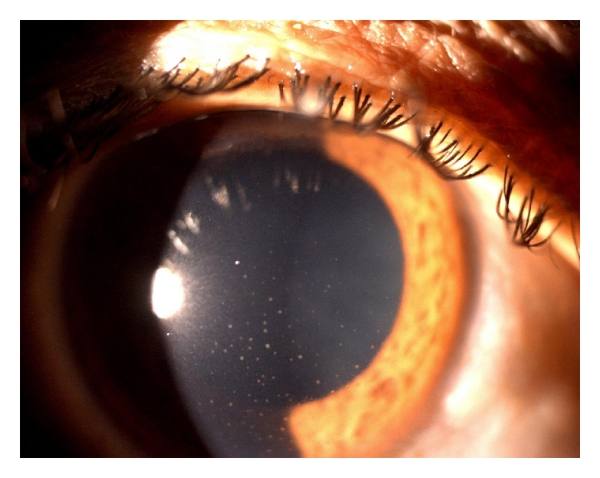
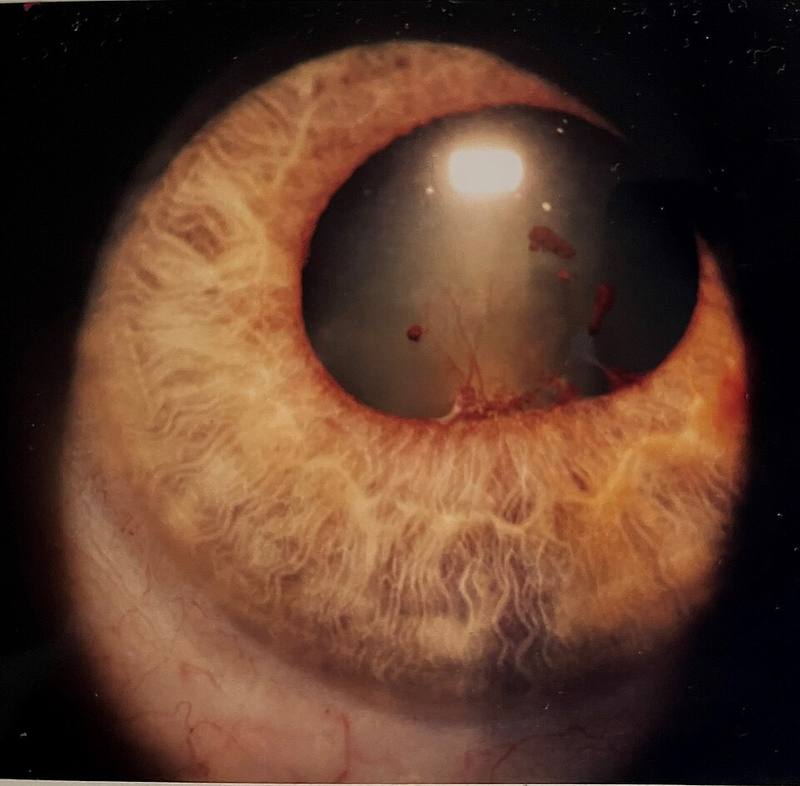
- Laterality and granulomatous features. After ruling out masquerade, clinical characterisation (unilateral vs bilateral, granulomatous vs non-granulomatous) is the main step of etiologic diagnosis [S5].
- HLA-B27 / spondyloarthritis pattern. Typically unilateral, with a marked tendency to recur, often alternating between eyes, and a good prognosis in most cases [S2]. Anterior uveitis is reported in at least 30% of people with spondyloarthritis, with a peak of 33.4% in ankylosing spondylitis; in inflammatory bowel disease-associated spondyloarthritis about 25%, and in psoriatic arthritis 2%-25% [S2]. Uveitis may precede the joint disease [S2].
- Viral patterns (overlap is considerable) [S6]:
- Granulomatous clusters of small and medium keratic precipitates in Arlt's triangle, with or without corneal scars: herpes simplex or varicella-zoster [S6].
- Few medium keratic precipitates, minimal cells and extremely high IOP (Posner-Schlossman syndrome): mainly cytomegalovirus [S6]. Attacks are recurrent, unilateral and non-granulomatous, mostly in middle-aged men [S3].
- Fuchs uveitis syndrome: fine stellate keratic precipitates across the endothelium, diffuse iris stromal atrophy and no posterior synechiae; mainly rubella or cytomegalovirus [S6].
- Cytomegalovirus anterior uveitis is highly prevalent in Asia and more common in men [S9]; it predominantly affects Asian males in the fifth to seventh decade, sometimes with coin-shaped keratic precipitates or nodular endothelial lesions [S6].
- Tubulointerstitial nephritis and uveitis (TINU) is under-recognised and occurs at all ages, not only in children [S4].
Confirm it
- Targeted routine tests. Chest radiography and serology for syphilis, HLA-B27 and angiotensin-converting enzyme are appropriate in severe, bilateral, recurrent or chronic anterior uveitis [S10].
- Further tests should follow clinical findings and regional epidemiology; untargeted investigations are of limited use and costly [S10].
- Aqueous humour analysis. Quantitative polymerase chain reaction (PCR) or the Goldmann-Witmer coefficient on aqueous helps confirm a viral cause and its severity, which guides treatment [S6] [S7].
- TINU. Urinary β2-microglobulin is a sensitive and specific screening test; the role of kidney biopsy in separating TINU from sarcoidosis is evolving [S4].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Anterior uveitis needs a full eye examination, including the posterior segment, to rule out infection and masquerade before treatment [S5]; refer rather than treat empirically (timing in the table below).
- People with ankylosing spondylitis, psoriatic arthritis or inflammatory bowel disease are at higher risk of anterior uveitis [S2]; recurrent episodes need an eye clinic each time [S2].
Tier B (general eye clinic)
- Characterise and exclude infection before steroids: laterality, granulomatous features, IOP, corneal signs and the posterior segment [S5] [S6].
- Topical treatment. Most isolated anterior uveitis resolves with topical corticosteroids [S10]. A BMJ Clinical Evidence systematic review graded the evidence on corticosteroid, mydriatic and non-steroidal anti-inflammatory eye drops for acute anterior uveitis, but its abstract does not report the effect sizes [S1]. Dosing is not covered by these abstracts: follow local formularies.
- Targeted tests for severe, bilateral, recurrent or chronic disease [S10].
- Comanage conventional IMT (methotrexate, azathioprine, mycophenolate mofetil) with rheumatology when steroids fail, cause limiting side effects, are needed at high doses, or there is systemic inflammatory disease [S10].
Tier C (specialist centre)
- Viral anterior uveitis. Confirm by aqueous PCR or Goldmann-Witmer coefficient [S6] [S7]. For cytomegalovirus anterior uveitis, early antiviral treatment reduces the risk of needing glaucoma surgery; oral valganciclovir and topical ganciclovir both produced positive outcomes, and an extended course could prevent relapse but should be limited to 6 months to limit resistance and side effects (narrative review) [S9]. Posner-Schlossman syndrome is often managed topically, but systemic therapy or surgery may be required [S3].
- Escalation. When quiescence is not reached on maximally tolerated antimetabolites, refer to a uveitis specialist for IMT escalation [S10]. Biologics have changed management of HLA-B27 and juvenile idiopathic arthritis-associated anterior uveitis [S5]; anti-tumour necrosis factor-α treatment of spondyloarthritis reduced anterior uveitis occurrence and flares [S2].
- Children with chronic anterior uveitis. Follow the 2023 MIWGUC update of the SHARE recommendations (14 consensus recommendations, >90% agreement) [S8].
- TINU. Management now includes systemic anti-inflammatory treatment for significant ocular and renal disease [S4].
Refer when
| Situation | Urgency |
|---|---|
| Suspected anterior uveitis seen without slit-lamp access | Same-day to an eye clinic |
| Anterior uveitis with markedly raised IOP, posterior segment involvement, suspected infection or masquerade, or a child with chronic anterior uveitis | Urgent to a uveitis specialist; timing per your local service or specialist advice [S5] [S6] [S8] [S9] |
| Uveitis not quiet despite maximally tolerated antimetabolites | Routine, at the next available uveitis clinic; timing depends on local factors [S10] |
Pitfalls
- Treating every anterior uveitis with steroids without excluding infection [S5].
- Missing a viral cause in hypertensive uveitis; cytomegalovirus anterior uveitis may progress to glaucoma without prompt treatment [S9].
- Ordering broad, untargeted test panels [S10].
- Not asking about back, joint, skin and bowel symptoms in recurrent unilateral disease [S2].
- Overlooking TINU in adults [S4].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2010 | Systematic review (BMJ Clinical Evidence, GRADE) |
| [S2] | 2015 | Narrative review |
| [S3] | 2017 | Narrative review |
| [S4] | 2017 | Narrative review |
| [S5] | 2018 | Narrative review |
| [S6] | 2019 | Narrative review |
| [S7] | 2020 | Narrative review (India and Singapore authors) |
| [S8] | 2023 | Consensus recommendations after systematic review (paediatric) |
| [S9] | 2023 | Narrative review |
| [S10] | 2025 | Narrative review |
- Thin evidence. The search sheet returned mostly Behçet's syndrome reviews; apart from one 2010 systematic review [S1] and a paediatric consensus [S8], the sources here are narrative reviews (expert opinion level).
- The only systematic review of eye drops [S1] is from 2010 and its abstract does not give effect sizes or a conclusion on which drop works best.
- The 6-month limit on cytomegalovirus antiviral courses is a review recommendation, not trial evidence [S9].
- Referral timing depends on local factors [S10]; the timings in "Refer when" need Editor-in-Chief confirmation.
- Not covered by these sources: symptoms at presentation, specific steroid and cycloplegic regimens and doses, steroid-induced IOP rise, management of herpetic anterior uveitis, and cost or access in low-resource settings.
Related articles
- Biologics and Immunosuppression for Non-infectious Uveitis
- Juvenile Idiopathic Arthritis-associated Uveitis
- Topical and periocular corticosteroids: benefits and risks
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Islam N, Pavesio C Uveitis (acute anterior). BMJ clinical evidence. (2010). PubMed 21736765
- [S2] Cantini F, Nannini C, Cassarà E, Kaloudi O, Niccoli L Uveitis in Spondyloarthritis: An Overview. The Journal of rheumatology. Supplement. (2015). PubMed 26523051 · doi:10.3899/jrheum.150630
- [S3] Megaw R, Agarwal PK Posner-Schlossman syndrome. Survey of ophthalmology. (2017). PubMed 28012873 · doi:10.1016/j.survophthal.2016.12.005
- [S4] Pakzad-Vaezi K, Pepple KL Tubulointerstitial nephritis and uveitis. Current opinion in ophthalmology. (2017). PubMed 28806188 · doi:10.1097/icu.0000000000000421
- [S5] Gueudry J, Muraine M Anterior uveitis. Journal francais d'ophtalmologie. (2018). PubMed 29290458 · doi:10.1016/j.jfo.2017.11.003
- [S6] Chan NS, Chee SP Demystifying viral anterior uveitis: A review. Clinical & experimental ophthalmology. (2019). PubMed 30345620 · doi:10.1111/ceo.13417
- [S7] Babu K, Konana VK, Ganesh SK, Patnaik G, Chan NSW, Chee SP, et al. Viral anterior uveitis. Indian journal of ophthalmology. (2020). PubMed 32823392 · doi:10.4103/ijo.ijo_928_20
- [S8] Foeldvari I, Maccora I, Petrushkin H, Rahman N, Anton J, de Boer J, et al. New and Updated Recommendations for the Treatment of Juvenile Idiopathic Arthritis-Associated Uveitis and Idiopathic Chronic Anterior Uveitis. Arthritis care & research. (2023). PubMed 35638697 · doi:10.1002/acr.24963
- [S9] Zhang J, Kamoi K, Zong Y, Yang M, Ohno-Matsui K Cytomegalovirus Anterior Uveitis: Clinical Manifestations, Diagnosis, Treatment, and Immunological Mechanisms. Viruses. (2023). PubMed 36680225 · doi:10.3390/v15010185
- [S10] Xie JS, Ocampo V, Kaplan AJ Anterior uveitis for the comprehensive ophthalmologist. Canadian journal of ophthalmology. Journal canadien d'ophtalmologie. (2025). PubMed 39128830 · doi:10.1016/j.jcjo.2024.07.013