Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Juvenile Idiopathic Arthritis-associated Uveitis
Juvenile idiopathic arthritis (JIA) is the most common chronic rheumatic disease of childhood and is associated with uveitis in up to 20-25% of cases [S8]. The uveitis is typically chronic, asymptomatic, non-granulomatous and anterior, so children must be found by screening rather than by symptoms [S8]. It is a leading cause of preventable visual loss in children [S10].
Key points - Screen children with JIA regularly; frequency should follow individual risk factors (younger age and positive antinuclear antibody at onset, oligoarticular subtype, short disease duration) [S3] [S7]. - Topical glucocorticoids are the initial treatment; methotrexate, then adalimumab, are added when systemic treatment is needed [S3] [S8]. - Adalimumab with methotrexate markedly lowers treatment failure or relapse (pooled hazard ratio 0.18) [S10]. - Stopping adalimumab after at least 1 year of control led to recurrence in 68% vs 14% who continued (ADJUST RCT) [S9]. - Management needs close collaboration between paediatric rheumatologist and ophthalmologist [S8].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- No symptoms does not mean no uveitis. Mild to moderate inflammation is asymptomatic in the initial stages [S1].
- Complications at diagnosis. Structural complications are present at diagnosis in 30% to 50% of children with JIA-associated uveitis (trial protocol background) [S1].
- Amblyopia risk. Delayed diagnosis, inadequate treatment and amblyopia contribute to the morbidity of childhood uveitis [S2].
- Missed screening. Strong monitoring recommendations were made because of vision-threatening complications with infrequent monitoring [S3].
- Flare after stopping adalimumab. Median time to failure after switching to placebo was 119 days [S9].
Recognise it: who is at risk
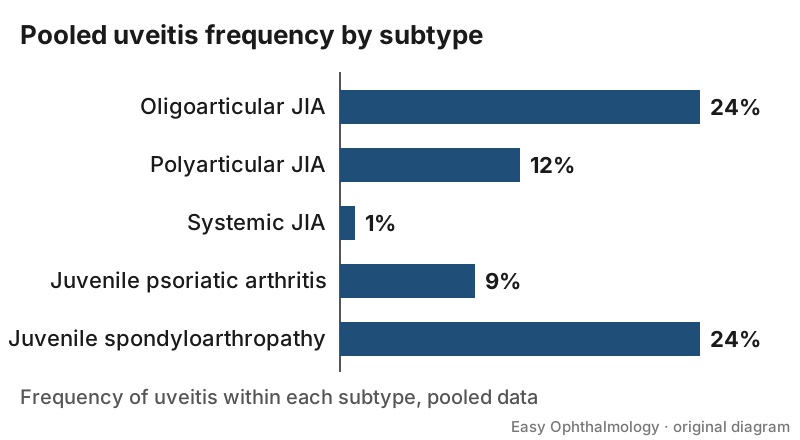
- By subtype. Pooled uveitis frequency was 24% in oligoarticular JIA, 12% in polyarticular JIA and 1% in systemic JIA; 9% in juvenile psoriatic arthritis and 24% in juvenile spondyloarthropathy [S4].
- Predictors. Younger age and positive antinuclear antibody at JIA onset, extended and persistent oligoarthritis, rheumatoid factor-negative polyarthritis, psoriatic arthritis and short JIA duration [S7]. Onset of arthritis under seven years of age is a major risk factor [S1].
- Geography. Uveitis in JIA was more common in Europe (14%), North America (11%) and the Middle East (12%) than in East Asia (7%) and Oceania (3%) [S4].
- Treatment effect on risk. Methotrexate and monoclonal TNF inhibitors reduce the risk of JIA uveitis [S7].
Confirm it
- The type is most often anterior uveitis (14% of JIA patients in pooled data) [S4], chronic and non-granulomatous [S8].
- Grade activity with Standardization of Uveitis Nomenclature (SUN) criteria; trials used SUN grading for success and failure [S1] [S6].
- Monitoring intervals should be based on examination findings and the treatment regimen [S3].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Every child diagnosed with JIA needs referral for ophthalmic screening, because uveitis is often silent [S1] [S3]. Children with none of the Nordic risk factors do not benefit from long-term screening [S7], but that judgement belongs to the eye and rheumatology team.
- Do not stop methotrexate or adalimumab without the treating team: stopping adalimumab caused frequent relapse [S9].
Tier B (general eye clinic)
- Screen by risk. Examine at intervals set by risk factors; children on TNF inhibitors or methotrexate may be screened less often [S7]. Exact intervals are in the Nordic and ACR guidelines, not in these abstracts [S3] [S7].
- Start topical glucocorticoids to control inflammation [S3]. Dosing is not covered by these abstracts: follow local formularies.
- Comanage with paediatric rheumatology for systemic therapy [S8].
- Watch for amblyopia and complications such as cataract and glaucoma [S1] [S2].
Tier C (specialist centre)
- Stepwise systemic therapy. Methotrexate first, adding adalimumab if methotrexate alone is not sufficient [S8]; the ACR guideline recommends methotrexate and the monoclonal TNF inhibitors adalimumab and infliximab when systemic treatment is needed [S3].
- Adalimumab evidence. Cochrane (3 RCTs, 134 participants, low certainty) found adalimumab increases treatment success (risk ratio 2.60) and decreases failure (risk ratio 0.23) vs placebo; evidence for etanercept was very limited [S6]. A 2026 meta-analysis of RCTs found a pooled hazard ratio of 0.18 for failure or relapse with adalimumab plus methotrexate [S10]. In SYCAMORE, adalimumab was dosed at 20 mg for patients under 30 kg or 40 mg for 30 kg or more, every 2 weeks, on stable methotrexate (as reported in [S1]).
- When to stop. In ADJUST (87 patients controlled for at least 1 year), treatment failure occurred in 14% continuing vs 68% stopping adalimumab; all who failed regained control after restarting, with a median of 105 days [S9]. Four serious adverse events occurred, all in the adalimumab group [S9].
- Refractory disease. Anti-IL6 agents or other anti-TNF agents such as infliximab may be considered, though evidence is limited [S8]. The 2023 MIWGUC update of SHARE provides 14 consensus treatment recommendations [S5].
Refer when
| Situation | Urgency |
|---|---|
| New diagnosis of JIA | Routine ophthalmic screening, of diagnosis; timing per your local service or specialist advice [S3] |
| Child with JIA and a red eye, reduced vision or a new squint | Urgent to an eye clinic; timing per your local service or specialist advice |
| Uveitis active despite topical steroid, or complications present | Urgent to paediatric uveitis and rheumatology care; timing per your local service or specialist advice [S3] [S8] |
Pitfalls
- Waiting for symptoms before examining a child with JIA [S1] [S8].
- Stopping screening after a normal first examination in a high-risk child [S3] [S7].
- Stopping adalimumab once quiet without planning for likely relapse [S9].
- Overlooking amblyopia in young children with uveitis [S2].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2014 | RCT protocol (SYCAMORE); background figures are not trial results |
| [S2] | 2016 | Narrative review (India) |
| [S3] | 2019 | ACR/Arthritis Foundation guideline (GRADE, largely expert consensus) |
| [S4] | 2019 | Meta-analysis, 59 studies |
| [S5] | 2023 | Consensus recommendations after systematic review |
| [S6] | 2022 | Cochrane systematic review, 3 RCTs |
| [S7] | 2023 | Nordic screening guideline |
| [S8] | 2024 | Narrative review |
| [S9] | 2025 | Multicentre RCT (ADJUST), stopped at interim, NIH funded |
| [S10] | 2026 | Meta-analysis of 3 RCTs |
- The ACR guideline states that recommendations rest on consensus expert opinion owing to low-quality evidence [S3].
- Conflict: Cochrane initial pooled estimates using standard SUN definitions showed little or no difference, whereas trial-specific definitions showed benefit [S6].
- The trials described were run in the USA, UK, France and Australia [S6] [S9]; uveitis frequency in JIA varies by region [S4].
- Not covered by these sources: exact screening intervals, methotrexate dosing, cataract and glaucoma surgery, and access to biologics in low-resource settings.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Ramanan AV, Dick AD, Benton D, Compeyrot-Lacassagne S, Dawoud D, Hardwick B, et al. A randomised controlled trial of the clinical effectiveness, safety and cost-effectiveness of adalimumab in combination with methotrexate for the treatment of juvenile idiopathic arthritis associated uveitis (SYCAMORE Trial). Trials. (2014). PubMed 24405833 · doi:10.1186/1745-6215-15-14
- [S2] Gupta A, Ramanan AV Uveitis in Children: Diagnosis and Management. Indian journal of pediatrics. (2016). PubMed 26420255 · doi:10.1007/s12098-015-1889-x
- [S3] Angeles-Han ST, Ringold S, Beukelman T, Lovell D, Cuello CA, Becker ML, et al. 2019 American College of Rheumatology/Arthritis Foundation Guideline for the Screening, Monitoring, and Treatment of Juvenile Idiopathic Arthritis-Associated Uveitis. Arthritis care & research. (2019). PubMed 31021540 · doi:10.1002/acr.23871
- [S4] Hayworth JL, Turk MA, Nevskaya T, Pope JE The frequency of uveitis in patients with juvenile inflammatory rheumatic diseases. Joint bone spine. (2019). PubMed 31207292 · doi:10.1016/j.jbspin.2019.06.001
- [S5] Foeldvari I, Maccora I, Petrushkin H, Rahman N, Anton J, de Boer J, et al. New and Updated Recommendations for the Treatment of Juvenile Idiopathic Arthritis-Associated Uveitis and Idiopathic Chronic Anterior Uveitis. Arthritis care & research. (2023). PubMed 35638697 · doi:10.1002/acr.24963
- [S6] Renton WD, Jung J, Palestine AG Tumor necrosis factor (TNF) inhibitors for juvenile idiopathic arthritis-associated uveitis. The Cochrane database of systematic reviews. (2022). PubMed 36239193 · doi:10.1002/14651858.cd013818.pub2
- [S7] Leinonen S A Nordic screening guideline for juvenile idiopathic arthritis-related uveitis. Acta ophthalmologica. (2023). PubMed 36458735 · doi:10.1111/aos.15299
- [S8] Maccora I, Simonini G, Guly CM, Ramanan AV Management of JIA associated uveitis. Best practice & research. Clinical rheumatology. (2024). PubMed 39048481 · doi:10.1016/j.berh.2024.101979
- [S9] Acharya NR, Ramanan AV, Coyne AB, Dudum KL, Rubio EM, Woods SM, et al. Stopping of adalimumab in juvenile idiopathic arthritis-associated uveitis (ADJUST): a multicentre, double-masked, randomised controlled trial. Lancet (London, England). (2025). PubMed 39863370 · doi:10.1016/s0140-6736(24)02468-1
- [S10] Alshehri AF, Alhazzani R, Almazrou AA, Almutairi FM, Barnawi AB, Aldail AA, et al. Initiation and Continuation of Adalimumab with Methotrexate for Juvenile Idiopathic Arthritis-Associated Uveitis: Systematic Review and Meta-Analysis of Randomized Controlled Trials. Ocular immunology and inflammation. (2026). PubMed 41945858 · doi:10.1080/09273948.2026.2646604