Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Bacterial keratitis
Bacterial keratitis is a sight-threatening corneal infection that, if not diagnosed and treated promptly, can cause corneal scarring, visual impairment and blindness [S11]. Nearly half of microbiologically confirmed infectious keratitis worldwide is bacterial, with trauma and contact lens wear as the main reported risk factors [S12]. Fungal keratitis is covered in its own article.
Key points - Broad-spectrum topical antibiotics are the primary treatment; local organism and resistance patterns should guide the choice [S11] [S12]. - Fluoroquinolone monotherapy and fortified antibiotic combinations gave similar cure rates in a meta-analysis of 9 RCTs [S9]; in a network meta-analysis ciprofloxacin healed slowest [S11]. - Adjunctive topical corticosteroids did not improve 3-month vision overall in the largest RCT (SCUT) [S1]; possible benefit appeared only in subgroups, and Nocardia ulcers did worse on steroids [S3] [S4]. - Where effective antibiotics are not available, povidone-iodine 1.25% was not significantly different from commonly available antibiotics in an RCT in the Philippines and India [S6]. - Adjuvant corneal cross-linking (CXL) is unproven for bacterial keratitis [S7] [S8].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
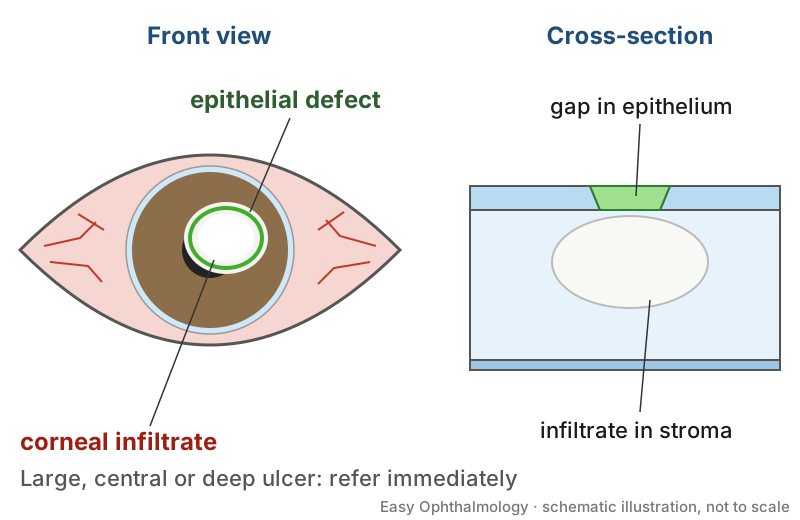
- Corneal infiltrate with an epithelial defect in a contact lens wearer or after trauma. These are the leading reported risk factors [S12].
- Suspected Pseudomonas. Pseudomonas aeruginosa made up 17% of isolates in a global review, which advises empirical therapy that covers it [S12].
- Possible MRSA or fluoroquinolone resistance. About 20% of S. aureus isolates were MRSA and fluoroquinolone susceptibility of S. aureus was about 77% in a global meta-analysis [S12].
- Steroids started without antibiotic cover or in Nocardia keratitis. Corticosteroids were associated with larger scars in Nocardia ulcers [S3].
- Worsening despite treatment. In one RCT 18.2% and 18.5% of ulcers worsened in both treatment arms [S2].
Recognise it
- Who is at risk. Reported risk factors include trauma (about 44%) and contact lens wear (about 23%) [S12]; a Cochrane review also lists ocular surface disease and previous ocular or eyelid surgery [S5].
- Burden. The pooled global proportion of bacterial keratitis among infectious keratitis was 44% (95% CI 39 to 49%), ranging from about 61% in Oceania to about 29% in Africa [S12]. Infectious keratitis rates are higher in low- and middle-income countries [S11].
- Organisms. Of about 25,000 isolates, 72% were Gram-positive; dominant species were S. epidermidis (15%), S. pneumoniae (13%), S. aureus (10%) and P. aeruginosa (17%) [S12].
Confirm it
- Corneal scraping for smear and culture identifies the organism so that the correct antibiotic can be started [S10].
- Instrument. In an RCT of 115 patients, a 26-gauge needle and a Kimura spatula gave comparable sample adequacy, staining, culture and safety; the needle gave more fully adequate samples in subgroup analysis and is cheap, disposable and needs no sterilisation unit [S10].
- Susceptibility. Gram-positive isolates showed more than 95% susceptibility to vancomycin and Gram-negative isolates more than 90% to aminoglycosides and cephalosporins [S12].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Recognise the red flags and refer early (see "Refer when").
- Where effective topical antibiotics are not an option, povidone-iodine 1.25% showed no significant difference from neomycin-polymyxin B-gramicidin (Philippines) or ciprofloxacin 0.3% (India) for time to presumed cure in a randomised, investigator-masked trial of 172 patients [S6]. The authors suggest it can be considered when antibiotic treatment is not practical [S6]. This is a single trial with wide confidence intervals [S6].
- Dosing schedules are not covered by these abstracts: follow local formularies.
Tier B (general eye clinic)
- Scrape before treating, where possible, with a 26-gauge needle if no spatula is available [S10].
- Start broad-spectrum topical antibiotics [S11]: - A meta-analysis of 9 RCTs (2024) found fluoroquinolones equivalent to fortified antibiotics for cure rate (OR 0.99, 95% CI 0.75 to 1.30) and adverse events (OR 0.75, 95% CI 0.48 to 1.17) [S9]. - In an equivalence RCT of 224 patients, moxifloxacin 0.5% healed 81.4% of moderate ulcers at 3 months versus 81.8% with fortified cefazolin 5% plus tobramycin 1.3%, as reported in [S2]. - A Cochrane network meta-analysis (2025; 23 RCTs, 2692 participants) ranked vancomycin plus ceftazidime, moxifloxacin, and cefazolin plus tobramycin as most effective for healing time, and ciprofloxacin as least effective; most evidence was of moderate to very low certainty [S11]. - Because about 20% of S. aureus isolates were MRSA, the global review recommends broad empirical therapy targeting MRSA and Pseudomonas [S12].
- Corticosteroids: specialist decision only. SCUT (500 patients, culture-positive ulcers, at least 48 hours of moxifloxacin before randomisation to prednisolone phosphate 1% or placebo) found no difference in 3-month vision, scar size, re-epithelialisation or perforation [S1]. A Cochrane review of 4 RCTs (611 participants) found inadequate evidence for benefit or harm [S5].
Tier C (specialist centre)
- Selective steroid use. In SCUT, steroids gave better 3-month vision in eyes with counting fingers or worse at baseline (0.17 logMAR) and with completely central ulcers (0.20 logMAR) [S1]. At 12 months, steroids were associated with about 1 line better vision in non-Nocardia ulcers but larger scars in Nocardia ulcers [S3]. Adding steroids after 2 to 3 days of antibiotics gave about 1 line better vision, whereas adding them after 4 or more days did not [S4]. These are subgroup analyses and need confirmation [S1] [S4].
- Cross-linking (PACK-CXL). A Cochrane review (3 trials, 59 eyes) found very low-certainty evidence and could not show benefit [S7]. The CLAIR RCT in India (smear-positive ulcers, moxifloxacin 0.5% with or without CXL) could not confirm a benefit, although fewer perforations or therapeutic keratoplasties occurred with CXL [S8].
Refer when
| Situation | Urgency |
|---|---|
| Suspected bacterial keratitis seen where scraping and broad-spectrum antibiotics are unavailable | Same-day to an eye clinic |
| Large, central or deep ulcer, vision counting fingers or worse, thinning or perforation | Immediate to a cornea specialist [G1] |
| Ulcer worsening or not improving on treatment | Within hours to a specialist centre |
Pitfalls
- Starting steroids early without a culture-proven bacterial diagnosis and antibiotic cover; SCUT enrolled only culture-positive ulcers already on moxifloxacin [S1].
- Assuming fluoroquinolone susceptibility: S. aureus susceptibility was about 77% [S12].
- Treating Nocardia ulcers with steroids [S3].
- Offering CXL as standard care: evidence is low certainty [S7] [S8].
- Skipping scraping because a spatula is unavailable: a 26-gauge needle performed comparably [S10].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2012 | Multicentre double-masked RCT (SCUT), 500 patients |
| [S2] | 2013 | Equivalence RCT, 224 patients |
| [S3] | 2014 | SCUT 12-month secondary outcomes |
| [S4] | 2014 | SCUT subgroup analysis by timing |
| [S5] | 2014 | Cochrane systematic review, 4 RCTs |
| [S6] | 2017 | Investigator-masked RCT, 172 patients |
| [S7] | 2020 | Cochrane systematic review, 3 trials |
| [S8] | 2021 | Outcome-masked RCT (CLAIR), India |
| [S9] | 2024 | Meta-analysis of 9 RCTs |
| [S10] | 2025 | Randomised pilot study, 115 patients |
| [S11] | 2025 | Cochrane network meta-analysis, 23 RCTs |
| [S12] | 2026 | Systematic review and meta-analysis of 58 observational studies |
- In the network meta-analysis, 12 studies were at high risk of bias and most results were not of high certainty [S11].
- The global prevalence estimate had very high heterogeneity (I² about 97%) and susceptibility data were synthesised descriptively [S12].
- All Cochrane steroid trials had losses to follow-up of 10% or more and three of four were underpowered [S5].
- Steroid benefit in SCUT comes from subgroup and secondary analyses, not the primary outcome [S1] [S3] [S4].
- The fluoroquinolone versus fortified meta-analysis [S9] and the network meta-analysis [S11] differ in emphasis: one found equivalence overall, the other ranked ciprofloxacin lowest for healing time.
- Not covered by these sources: dosing frequency and duration, preparation of fortified drops, contact lens hygiene advice, surgical management of perforation, and outcomes of therapeutic keratoplasty.
Related articles
- Fungal keratitis
- Acanthamoeba keratitis
- Contact lens complications and safe wear
- Ocular antibiotics and antimicrobial resistance
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Srinivasan M, Mascarenhas J, Rajaraman R, Ravindran M, Lalitha P, Glidden DV, et al. Corticosteroids for bacterial keratitis: the Steroids for Corneal Ulcers Trial (SCUT). Archives of ophthalmology (Chicago, Ill. : 1960). (2012). PubMed 21987582 · doi:10.1001/archophthalmol.2011.315
- [S2] Sharma N, Goel M, Bansal S, Agarwal P, Titiyal JS, Upadhyaya AD, et al. Evaluation of moxifloxacin 0.5% in treatment of nonperforated bacterial corneal ulcers: a randomized controlled trial. Ophthalmology. (2013). PubMed 23415776 · doi:10.1016/j.ophtha.2012.11.013
- [S3] Srinivasan M, Mascarenhas J, Rajaraman R, Ravindran M, Lalitha P, O'Brien KS, et al. The steroids for corneal ulcers trial (SCUT): secondary 12-month clinical outcomes of a randomized controlled trial. American journal of ophthalmology. (2014). PubMed 24315294 · doi:10.1016/j.ajo.2013.09.025
- [S4] Ray KJ, Srinivasan M, Mascarenhas J, Rajaraman R, Ravindran M, Glidden DV, et al. Early addition of topical corticosteroids in the treatment of bacterial keratitis. JAMA ophthalmology. (2014). PubMed 24763755 · doi:10.1001/jamaophthalmol.2014.292
- [S5] Herretes S, Wang X, Reyes JM Topical corticosteroids as adjunctive therapy for bacterial keratitis. The Cochrane database of systematic reviews. (2014). PubMed 25321340 · doi:10.1002/14651858.cd005430.pub3
- [S6] Isenberg SJ, Apt L, Valenton M, Sharma S, Garg P, Thomas PA, et al. Prospective, Randomized Clinical Trial of Povidone-Iodine 1.25% Solution Versus Topical Antibiotics for Treatment of Bacterial Keratitis. American journal of ophthalmology. (2017). PubMed 27984024 · doi:10.1016/j.ajo.2016.10.004
- [S7] Davis SA, Bovelle R, Han G, Kwagyan J Corneal collagen cross-linking for bacterial infectious keratitis. The Cochrane database of systematic reviews. (2020). PubMed 32557558 · doi:10.1002/14651858.cd013001.pub2
- [S8] Prajna NV, Radhakrishnan N, Lalitha P, Rajaraman R, Narayana S, Austin AF, et al. Cross-Linking Assisted Infection Reduction (CLAIR): A Randomized Clinical Trial Evaluating the Effect of Adjuvant Cross-Linking on Bacterial Keratitis. Cornea. (2021). PubMed 33079921 · doi:10.1097/ico.0000000000002510
- [S9] Zhou R, Wang Q, Yuan L, Zhou H, Xue J Safety and efficacy of fortified antibiotics and fluoroquinolones for the treatment of bacterial keratitis: A meta-analysis. Journal francais d'ophtalmologie. (2024). PubMed 37741755 · doi:10.1016/j.jfo.2023.01.046
- [S10] Maharana PK, Bari A, Mandal S, Pillai SS, Hussain N, Sinha R, et al. Comparative Evaluation of 26-Gauge Needle Versus Kimura Spatula for Corneal Scraping in Infective Keratitis: A Randomized Controlled Trial. Eye & contact lens. (2025). PubMed 40605178 · doi:10.1097/icl.0000000000001203
- [S11] Song A, Yang Y, Henein C, Bunce C, Qureshi R, Ting DSJ Topical antibiotics for treating bacterial keratitis: a network meta-analysis. The Cochrane database of systematic reviews. (2025). PubMed 40728038 · doi:10.1002/14651858.cd015350.pub2
- [S12] Singh RB, Singh Parmar UP, Woreta F, Srikumaran D, Sharma N, Jhanji V Global burden, risk factors, causative organisms and antibiotic susceptibility patterns in bacterial keratitis. The ocular surface. (2026). PubMed 41422890 · doi:10.1016/j.jtos.2025.12.003
Guidelines
- [G1] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 5.12 Keratitis, Microbial, Bacterial (2026). https://www.eyes.nhs.scot/eyecare-guidelines/section-5-corneal/512-keratitis-microbial-bacterial/