Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Ocular Toxoplasmosis
Ocular toxoplasmosis, caused by the parasite Toxoplasma gondii, is the leading cause of posterior uveitis globally; it recurs and can cause visual impairment and blindness [S9]. Recurrences occur in about half of patients, and visual impairment in 35% and blindness in 20% of eyes in pooled data [S9]. Treatment reduces recurrence, but no antibiotic regimen has been shown to be superior, so choice depends on safety, sulfa allergy and availability [S3] [S8].
Key points - Expert consensus (2025, 103 uveitis experts) supports antiparasitic therapy in most active cases, PCR only for atypical presentations, and prophylaxis in high-risk scenarios [S11]. - No antibiotic regimen was superior to the others in a meta-analysis of RCTs; choose by safety, sulfa allergy and availability [S8]. - Long-term trimethoprim-sulfamethoxazole (TMP-SMZ) after an active episode reduced recurrence in Brazilian RCTs [S7] [S9]. - Corticosteroids without anti-toxoplasma cover can precipitate fulminant infection when toxoplasmosis is mistaken for viral retinitis [S12]. - Antifolate regimens cannot be used routinely in pregnancy, especially in the first trimester [S10].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Lesion near the macula or adjacent to the optic nerve. Odds ratio 4.83 for blindness [S9].
- More than one recurrence. Odds ratio 3.18 for blindness [S9].
- Immunocompromised or steroid-exposed patient with necrotising retinitis. Toxoplasmosis can masquerade as acute retinal necrosis or cytomegalovirus retinitis; in a case-based review, 79.1% were immunocompromised, the mean diagnostic delay was 26.4 days, and over half the eyes ended worse than 20/200 [S12].
- Pregnancy. Treatment choice must consider the fetus [S10].
Recognise it
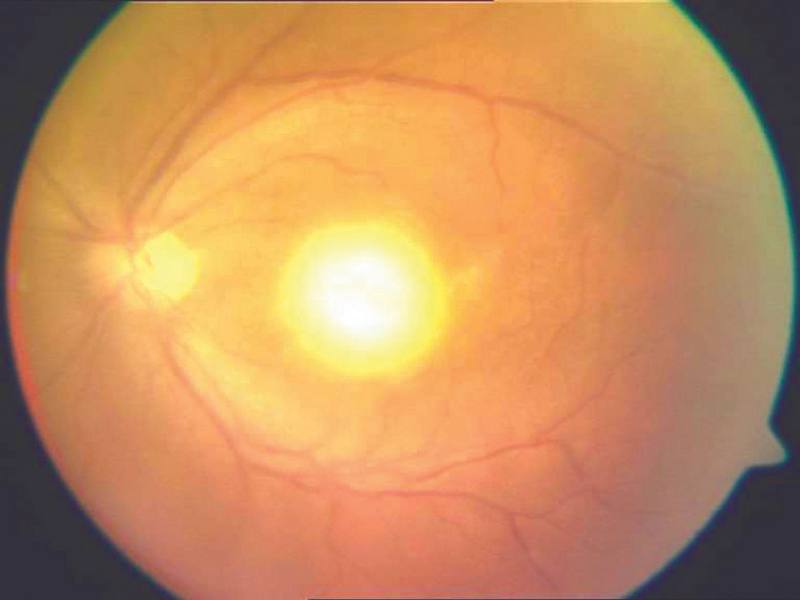
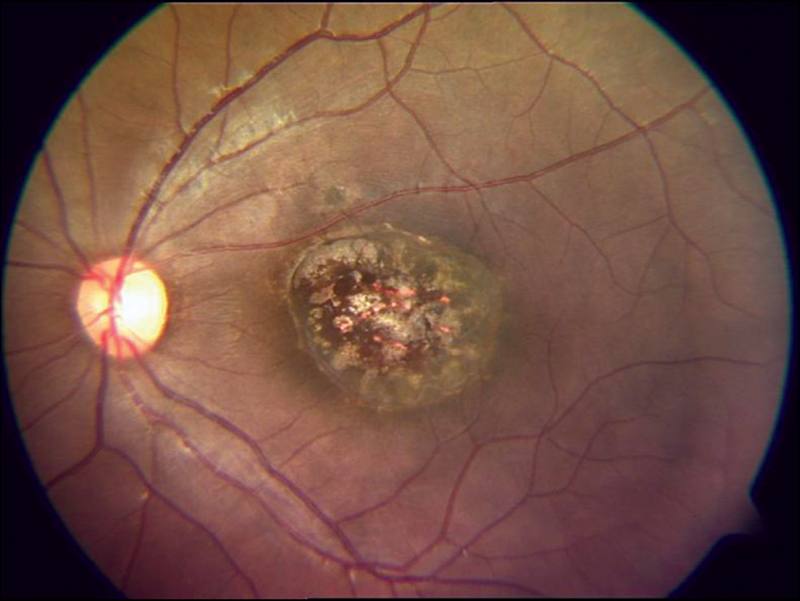
- Risk factors for recurrence: age over 40 years, de novo lesions or less than one year since the first episode, macular involvement, lesions larger than 1 disc diameter, congenital toxoplasmosis and bilateral disease [S9].
- Recurrences were more frequent in South American than European populations [S9].
- Complications include glaucoma, cataract and posterior synechiae [S4].
Confirm it
- In acute posterior uveitis suspected to be toxoplasmic, serological testing should always be obtained [S6].
- Reserve PCR for atypical presentations [S11]; in masquerade cases diagnosis came from serum serology (48.8%) or intraocular fluid PCR (34.9%) [S12].
- In pregnancy, serologic and intraocular fluid testing may improve diagnostic accuracy [S10].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Do not give systemic or local corticosteroids for a suspected retinitis without anti-toxoplasma cover; empiric steroids worsened outcomes in masquerade cases [S12].
- Refer any patient with new floaters or reduced vision and a history of toxoplasmosis (timing in the table below).
Tier B (general eye clinic)
- Treat active disease. Antiparasitic therapy is supported in most active cases [S11]. A review recommends at least two drugs plus corticosteroids for active chorioretinitis, for at least 6 weeks [S6]. A Cochrane review found that antibiotics probably reduce recurrence (risk ratio 0.26, moderate certainty) but there is no good evidence of better vision [S3].
- Choose a regimen you can supply and monitor. No regimen was superior in a meta-analysis of RCTs (low to very low quality evidence) [S8]. Options studied include: - TMP-SMZ 160 mg/800 mg twice daily for 45 days, as reported in [S7]. - Pyrimethamine-based therapy: adverse events led to treatment change or discontinuation in all ocular studies reviewed; bone marrow suppression occurred in up to 9.0% in ocular toxoplasmosis, and Stevens-Johnson syndrome was reported in two ocular patients [S5]. Monitor blood counts [S5]. - Azithromycin 500 mg daily (as reported in [S2]) was effective and better tolerated than sulfadiazine-pyrimethamine in a 19-patient pilot RCT for non-vision-threatening lesions, though healing took longer [S2].
- Corticosteroids. Cochrane found no RCT evidence for or against adjunctive steroids [S4]; consensus and reviews still pair them with antiparasitics [S6]. Dosing is not covered by these abstracts: follow local formularies.
Tier C (specialist centre)
- Intravitreal clindamycin plus dexamethasone. In an Iranian RCT of 68 patients, 1 mg clindamycin and 400 μg dexamethasone (1 to 3 injections, as reported in [S1]) reduced lesion size as much as 6 weeks of pyrimethamine, sulfadiazine and prednisolone (57.0% vs 58.4%) [S1]. Intravitreal clindamycin gave a statistically significant but clinically irrelevant acuity advantage in pooled data [S8].
- Prophylaxis for frequent recurrence. In a Brazilian RCT of 141 patients, TMP-SMZ every other day for 311 days after initial treatment gave a 6-year cumulative recurrence of 1.4% vs 27.5% with placebo, with no treatment-limiting toxicity [S7]. Pooled protection was 83% in the first year and 87% in the second [S9].
- Pregnancy. Spiramycin and intravitreal treatment are alternatives discussed when antifolates are unsuitable [S10]. Women with acute infection in pregnancy and retinitis should be treated for the eye and to prevent vertical transmission [S6].
- Atypical or immunocompromised cases. Use early intraocular fluid PCR and avoid steroids without anti-toxoplasma coverage [S12].
Refer when
| Situation | Urgency |
|---|---|
| Suspected active lesion near the macula or optic nerve | Same-day to an eye specialist [EIC expert opinion] [S9] |
| Necrotising retinitis in an immunocompromised patient, or not responding to antiviral treatment | Immediate specialist assessment with intraocular PCR [EIC expert opinion] [S12] |
| Pregnant woman with active retinitis | Urgent to uveitis and obstetric care; timing per your local service or specialist advice [S6] [S10] |
Pitfalls
- Treating presumed viral retinitis with steroids alone [S12].
- Using pyrimethamine without blood monitoring [S5].
- Promising visual benefit from antibiotics; the proven effect is on recurrence [S3].
- Starting antifolates in early pregnancy [S10].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2011 | RCT, 68 patients, Iran |
| [S2] | 2012 | Pilot RCT, 19 patients |
| [S3] | 2016 | Cochrane review, 4 RCTs |
| [S4] | 2017 | Cochrane review, no eligible trials |
| [S5] | 2017 | Systematic review of adverse events, 31 studies |
| [S6] | 2019 | Systematic review of 11 randomised studies with practical guidance |
| [S7] | 2020 | RCT, 141 patients, Brazil, 6-year follow-up |
| [S8] | 2021 | Meta-analysis of RCTs comparing regimens |
| [S9] | 2023 | Meta-analysis of risk factors, 4,200 patients [S9] |
| [S10] | 2024 | Narrative review, pregnancy |
| [S11] | 2025 | Delphi consensus (Asia-Pacific and TITAN) |
| [S12] | 2026 | Systematic review of case reports and series, very low certainty |
- Most risk-factor data come from South America and Europe; only one study was from Africa [S9].
- Steroid use rests on consensus; there is no RCT evidence [S4].
- The masquerade review is based on case reports subject to selection and publication bias [S12].
- Not covered by these sources: congenital toxoplasmosis management in infants, HIV-specific regimens, and doses of pyrimethamine, sulfadiazine, clindamycin and steroids.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Soheilian M, Ramezani A, Azimzadeh A, Sadoughi MM, Dehghan MH, Shahghadami R, et al. Randomized trial of intravitreal clindamycin and dexamethasone versus pyrimethamine, sulfadiazine, and prednisolone in treatment of ocular toxoplasmosis. Ophthalmology. (2011). PubMed 20708269 · doi:10.1016/j.ophtha.2010.04.020
- [S2] Balaskas K, Vaudaux J, Boillat-Blanco N, Guex-Crosier Y Azithromycin versus Sulfadiazine and Pyrimethamine for non-vision-threatening toxoplasmic retinochoroiditis: a pilot study. Medical science monitor : international medical journal of experimental and clinical research. (2012). PubMed 22534709 · doi:10.12659/msm.882735
- [S3] Pradhan E, Bhandari S, Gilbert RE, Stanford M Antibiotics versus no treatment for toxoplasma retinochoroiditis. The Cochrane database of systematic reviews. (2016). PubMed 27198629 · doi:10.1002/14651858.cd002218.pub2
- [S4] Jasper S, Vedula SS, John SS, Horo S, Sepah YJ, Nguyen QD Corticosteroids as adjuvant therapy for ocular toxoplasmosis. The Cochrane database of systematic reviews. (2017). PubMed 28125765 · doi:10.1002/14651858.cd007417.pub3
- [S5] Ben-Harari RR, Goodwin E, Casoy J Adverse Event Profile of Pyrimethamine-Based Therapy in Toxoplasmosis: A Systematic Review. Drugs in R&D. (2017). PubMed 28879584 · doi:10.1007/s40268-017-0206-8
- [S6] Cortés JA, Roncancio Á, Uribe LG, Cortés-Luna CF, Montoya JG Approach to ocular toxoplasmosis including pregnant women. Current opinion in infectious diseases. (2019). PubMed 31313714 · doi:10.1097/qco.0000000000000577
- [S7] Fernandes Felix JP, Cavalcanti Lira RP, Grupenmacher AT, Assis Filho HLG, Cosimo AB, Nascimento MA, et al. Long-term Results of Trimethoprim-Sulfamethoxazole Versus Placebo to Reduce the Risk of Recurrent Toxoplasma gondii Retinochoroiditis. American journal of ophthalmology. (2020). PubMed 31926883 · doi:10.1016/j.ajo.2019.12.025
- [S8] Feliciano-Alfonso JE, Muñoz-Ortiz J, Marín-Noriega MA, Vargas-Villanueva A, Triviño-Blanco L, Carvajal-Saiz N, et al. Safety and efficacy of different antibiotic regimens in patients with ocular toxoplasmosis: systematic review and meta-analysis. Systematic reviews. (2021). PubMed 34275483 · doi:10.1186/s13643-021-01758-7
- [S9] Cifuentes-González C, Rojas-Carabali W, Pérez ÁO, Carvalho É, Valenzuela F, Miguel-Escuder L, et al. Risk factors for recurrences and visual impairment in patients with ocular toxoplasmosis: A systematic review and meta-analysis. PloS one. (2023). PubMed 37011101 · doi:10.1371/journal.pone.0283845
- [S10] Artiaga JCM, Azarcon CP, Levina FD, Bromeo AJ, Mesina BVQ, Arcinue CA Considerations in the management of ocular toxoplasmosis in pregnancy: a review of literature. Eye (London, England). (2024). PubMed 38191658 · doi:10.1038/s41433-023-02916-y
- [S11] Putera I, Cifuentes-González C, Rojas-Carabali W, Thng ZX, Murugan SB, Song R, et al. Controversy and consensus on the management of ocular toxoplasmosis: A joint statement by the Asia-Pacific Society of Ocular Inflammation and Infection (APSOII), the Asia-Pacific Vitreo-Retina Society (APVRS), the Academy of Asia-Pacific Professors of Ophthalmology (AAPPO) and The Infectious Uveitis Treatment Algorithm Network (TITAN) Group. Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2025). PubMed 40953705 · doi:10.1016/j.apjo.2025.100244
- [S12] Mikhail D, Macaron R, Coblentz J, Feltrin de Barros G, Burnier MN Ocular Toxoplasmosis Masquerading as Acute Retinal Necrosis and Cytomegalovirus Retinitis: A Systematic Review. Ophthalmology. Retina. (2026). PubMed 42749022 · doi:10.1016/j.oret.2026.09.004