Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Presbyopia-correcting and EDOF intraocular lenses
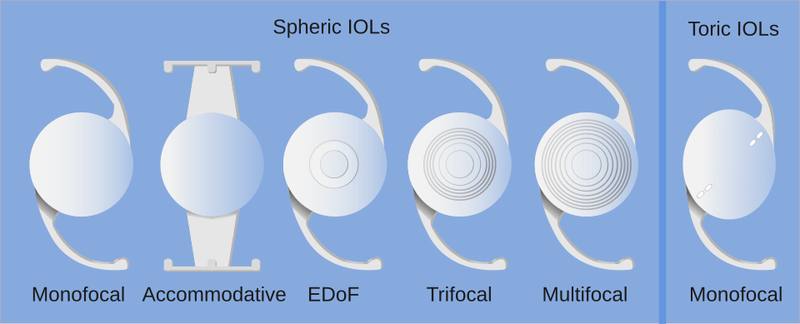
Presbyopia-correcting IOLs (bifocal and trifocal multifocal, extended depth of focus [EDOF] and accommodative lenses) aim to reduce spectacle dependence after cataract surgery [S1] [S8]. They improve near and intermediate vision compared with monofocal IOLs, but at the cost of more glare and haloes, so patient selection and counselling matter [S1] [S8] [S10].
Key points - Multifocal IOLs give distance vision similar to monofocal IOLs, better near vision and less spectacle dependence (RR 0.63), but more haloes (RR 3.58) and glare (RR 1.41) [S1]. - Trifocal and EDOF lenses give similar distance acuity; trifocals may give better near vision [S5]. Trifocals may improve intermediate vision compared with bifocals [S3]. - Compared with monovision, bilateral multifocal IOLs more often gave complete spectacle independence (RR 2.06) but more glare [S6]. - Even low residual astigmatism (0.5 D or more) significantly worsens distance and intermediate acuity after multifocal implantation [S4]. - Most evidence is low certainty, short term and from high-income settings; cost-effectiveness is context-dependent, with little data from low- and middle-income countries [S5] [S7] [S9].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Patient expectations not explored: no study correlated patient-reported outcomes with expectations [S2].
- Troublesome haloes and glare after surgery: more common and more troublesome with multifocal IOLs [S1]; in one trial more multifocal patients had IOL exchange in the first year (6 vs 0 with monovision) [S1].
- Uncorrected astigmatism: degrades results [S4].
- Low-light and glare conditions: contrast sensitivity is worse with multifocal lenses [S2].
Recognise it: who may benefit
- Motivation to achieve spectacle independence is likely to be the deciding factor [S1].
- Patients reported high overall satisfaction regardless of the lens implanted [S2].
- Trials excluded people with ocular comorbidities such as glaucoma, diabetes, macular degeneration or myopic retinopathy, so results apply to otherwise healthy eyes [S7].
Confirm it: preoperative assessment
- Evaluate astigmatism accurately before and after surgery [S4].
- An international consensus (AAPPO, 2026; 47 statements, 46 with over 75% agreement) covers refractive vs diffractive designs, blur and haloes, dysphotopsia, neuroadaptation and factors affecting success [S10].
Manage it: choosing a lens
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Tier A / Tier B / Tier C tiers apply only partly: presbyopia-correcting IOLs are an elective, usually self-paid option. At Tier A, explain that standard monofocal surgery with reading spectacles remains the usual, lower-cost result [S1] [S9].
Tier B (general eye clinic)
- Offer a monofocal IOL as the default; discuss multifocal options only where the lenses, accurate biometry and astigmatism management are available [S1] [S4].
- Monovision is an alternative: it caused less glare than bilateral multifocal IOLs (RR 0.343) with similar distance and near acuity [S6], though studies did not always target enough myopia in the near eye [S2].
Tier C (specialist centre)
- Multifocal vs monofocal. Cochrane (2016), 20 RCTs (3194 eyes): near vision better (RR for unaided near acuity worse than J3/J4 0.20, low certainty), distance similar (moderate certainty) [S1].
- Trifocal vs bifocal. Cochrane (2023), 7 RCTs (331 participants): better uncorrected intermediate acuity at one year (MD -0.16 logMAR, low certainty), no difference in distance or near [S3].
- Trifocal vs EDOF. Cochrane (2024), 5 studies (466 eyes): similar distance acuity; uncorrected near worse than J2 in 3% (trifocal) vs 30% (EDOF) in one study; glare and haloes with both [S5]. An overview of 8 systematic reviews agreed: multifocals better at near but with more glare and haloes; EDOF may offer spectacle independence without consistently matching near vision [S8].
- Mix-and-match (trifocal in one eye, EDOF in the other): favourable 3-month binocular acuity at all distances in 5 studies (225 patients), with very low certainty [S11].
- Accommodative IOLs: no extra dysphotopsia or contrast loss but only modest gains in spectacle independence [S2].
- Refractive lens exchange without cataract: a Cochrane review (2025) of 4 RCTs found only low or very low certainty evidence over 3 to 6 months [S7].
Refer when
| Situation | Urgency |
|---|---|
| Pain, redness or falling vision after surgery (possible infection or inflammation, as with any IOL) | Immediate, same-day [G1] |
| Persistent disabling glare, haloes or blur after a multifocal IOL | Routine to the implanting surgeon or a refractive cataract service; timing per your local service or specialist advice [S1] |
| Patient requests a presbyopia-correcting IOL | Routine, before listing, to a centre offering counselling and biometry [S10] |
Pitfalls
- Promising complete spectacle independence; results vary and adverse visual phenomena are common [S1] [S5].
- Ignoring 0.5 D of residual astigmatism [S4].
- Implanting multifocal IOLs in eyes with comorbidities excluded from trials [S7].
- Assuming high-income cost-effectiveness data apply elsewhere [S9].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2016 | Cochrane systematic review, 20 RCTs |
| [S2] | 2017 | Systematic review |
| [S3] | 2023 | Cochrane systematic review, 7 RCTs |
| [S4] | 2023 | Meta-analysis of 9 studies, including case series |
| [S5] | 2024 | Cochrane systematic review, 5 studies |
| [S6] | 2025 | Network meta-analysis, 32 studies |
| [S7] | 2025 | Cochrane systematic review, 4 RCTs |
| [S8] | 2025 | Overview of 8 systematic reviews |
| [S9] | 2025 | Systematic review of 14 economic evaluations |
| [S10] | 2026 | International expert consensus (25 experts) |
| [S11] | 2026 | Meta-analysis of 5 studies |
- In [S3], two trials received manufacturer funding and an author of another received lecture payments from lens manufacturers.
- None of the 8 reviews in [S8] met all AMSTAR-2 items; none reported cost-effectiveness [S8], whereas [S9] found multifocal IOLs cost-effective in high-income health systems, with LMIC evidence missing.
- Trial follow-up was mostly 3 to 12 months; long-term outcomes are not covered [S3] [S5] [S7].
- Not covered by these sources: specific lens models' performance beyond those named, pupil and angle kappa criteria, retinal disease and multifocal IOLs, and management of neuroadaptation failure.
Related articles
- Biometry and IOL power calculation
- Pharmacological treatment of presbyopia
- Phacoemulsification: outcomes and techniques
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] de Silva SR, Evans JR, Kirthi V, Ziaei M, Leyland M Multifocal versus monofocal intraocular lenses after cataract extraction. The Cochrane database of systematic reviews. (2016). PubMed 27943250 · doi:10.1002/14651858.cd003169.pub4
- [S2] Wang SY, Stem MS, Oren G, Shtein R, Lichter PR Patient-centered and visual quality outcomes of premium cataract surgery: a systematic review. European journal of ophthalmology. (2017). PubMed 28574135 · doi:10.5301/ejo.5000978
- [S3] Zamora-de La Cruz D, Bartlett J, Gutierrez M, Ng SM Trifocal intraocular lenses versus bifocal intraocular lenses after cataract extraction among participants with presbyopia. The Cochrane database of systematic reviews. (2023). PubMed 36705482 · doi:10.1002/14651858.cd012648.pub3
- [S4] Shen W, Zhuo B, Zhang L, Shen J, Ma D, Yang J Effect of astigmatism on visual outcomes after multifocal intraocular lens implantation: a systematic review and meta-analysis. Frontiers in medicine. (2023). PubMed 38089878 · doi:10.3389/fmed.2023.1214714
- [S5] Tavassoli S, Ziaei H, Yadegarfar ME, Gokul A, Kernohan A, Evans JR, et al. Trifocal versus extended depth of focus (EDOF) intraocular lenses after cataract extraction. The Cochrane database of systematic reviews. (2024). PubMed 38984608 · doi:10.1002/14651858.cd014891.pub2
- [S6] Hong ASY, Jin E, Shen L, Chen DZ Monovision versus multifocality for presbyopia during primary phacoemulsification: systematic review and network meta-analysis. Eye (London, England). (2025). PubMed 39548216 · doi:10.1038/s41433-024-03454-x
- [S7] Alvarado-Villacorta R, Yim TW, Hernandez-Quintela E, De La Torre-Gonzalez E, Loza Munarriz CA, Martinez-Zapata MJ Surgical interventions for presbyopia. The Cochrane database of systematic reviews. (2025). PubMed 40226888 · doi:10.1002/14651858.cd015711.pub2
- [S8] Daka Q, Henein C, Fang CEH, Mustafa R, Cocaj E, Azuara-Blanco A, et al. Effectiveness of intraocular lenses designed to correct presbyopia after cataract surgery: an overview of systematic reviews. The British journal of ophthalmology. (2025). PubMed 40623803 · doi:10.1136/bjo-2025-327363
- [S9] Wu Z, Cheng F, Xu J Economic Evaluation of Intraocular Lens Targeting Cataract Patients: A Review and Future Directions. Translational vision science & technology. (2025). PubMed 40838946 · doi:10.1167/tvst.14.8.30
- [S10] Rao SK, Safran SG, Gatinel D, Srinivas SP, Miller KM, Leung HYE, et al. International consensuses and guidelines on multifocal intraocular lenses (IOLs) by the Academy of Asia-Pacific Professors of Ophthalmology (AAPPO). Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2026). PubMed 41419160 · doi:10.1016/j.apjo.2025.100274
- [S11] Rakhimova M, Aldasheva N, Auyezova A, Orazbekov L, Utelbayeva Z, Svetlanova S, et al. Visual Outcomes After Mix-and-Match Implantation of Trifocal and Extended Depth-of-Focus Intraocular Lenses: A Systematic Review and Meta-Analysis. Medicina (Kaunas, Lithuania). (2026). PubMed 42356124 · doi:10.3390/medicina62061112
Guidelines
- [G1] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 7.4 Endophthalmitis, Post-Operative, (Exogenous Endophthalmitis) (2026). https://www.eyes.nhs.scot/eyecare-guidelines/section-7-uvea/74-endophthalmitis-post-operative-exogenous-endophthalmitis/