Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Scleritis
Scleritis is a serious, often painful inflammation of the sclera that can cause permanent loss of vision in severe cases [S1]. Most cases are immune mediated, and 30%-40% of patients have an underlying systemic autoimmune condition [S1]; rheumatoid arthritis and granulomatosis with polyangiitis (GPA) are the commonest associations of necrotising scleritis [S11]. A minority are infectious, and steroids given for presumed immune scleritis can spread the infection, so telling the two apart is critical [S6].
Key points - Subtypes are diffuse anterior, nodular anterior, necrotising and posterior scleritis [S9]; necrotising scleritis is the most destructive form [S11]. - Every patient needs a thorough systemic evaluation; scleritis may be the first sign of GPA or rheumatoid arthritis [S1]. - Infectious scleritis makes up 5%-10% of cases and needs directed antimicrobial therapy [S4]; test for syphilis [S12]. - Oral NSAIDs and oral corticosteroids are first-line for non-infectious scleritis; refractory cases need antimetabolites, T-cell inhibitors or biologics (expert opinion) [S2]. - Most treatment decisions rest on observational data; no head-to-head or refractory-case RCTs exist [S5].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Necrotising scleritis. Highest complication rates, with more secondary glaucoma and cataract than other forms [S11].
- Scleritis after eye surgery. Surgery is the commonest risk factor for infectious necrotising scleritis, most often caused by Pseudomonas [S11].
- Worsening on corticosteroids. Consider infection; steroids can propagate it [S6].
- Possible GPA: ocular involvement in GPA includes scleritis, orbital mass, dacryocystitis and keratitis [S10].
- Posterior scleritis. It can be sight-threatening and may cause choroidal folds, effusion and exudative retinal detachment [S8].
Recognise it
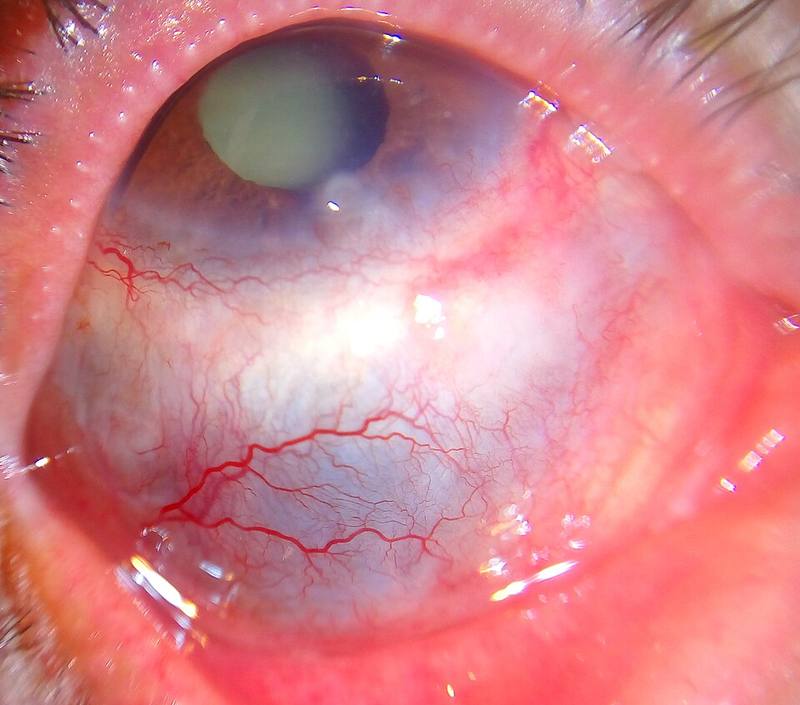
- Symptoms and signs. Focal or diffuse hyperaemia, moderate to severe pain and frequent visual impairment [S4]; severe ocular pain and tissue destruction [S6].
- Course. Acute monophasic, relapsing-remitting or chronic [S1].
- Episcleritis vs scleritis. Prompt discrimination matters because management, prognosis and complications differ [S3].
- Associations. Rheumatoid arthritis, inflammatory bowel disease, systemic lupus erythematosus and GPA [S9]; ANCA-associated vasculitis and IgG4-related disease [S5]. About half of patients have no identifiable cause [S1].
- Posterior scleritis can involve the choroid: increased thickness, choroidal vasculitis, a choroidal or subretinal mass, choroidal folds, effusion or exudative detachment [S8].
Confirm it
- Systemic work-up guided by careful history and examination [S3]; all patients require thorough systemic evaluation [S1].
- ANCA serology supports a diagnosis of GPA together with imaging and biopsy [S10].
- Syphilis testing for every patient with scleritis or episcleritis is important, given rising global incidence [S12].
- Suspected infection: culture or biopsy; Nocardia was diagnosed on excisional biopsy of a scleral nodule in one case [S4].
- Posterior scleritis: multimodal imaging helps diagnosis and monitoring [S8].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Severe eye pain with redness or reduced vision, especially in a patient with rheumatoid arthritis or vasculitis, needs eye specialist assessment (timing in the table below) [S1] [S5].
- Do not start steroid eye drops or oral steroids before infection has been considered; steroids can spread infectious scleritis [S6].
Tier B (general eye clinic)
- Classify the subtype and look for necrosis [S9] [S11].
- Exclude infection, including syphilis [S6] [S12].
- First-line for non-necrotising, non-infectious disease: oral NSAIDs [S9]; local subconjunctival steroid injection is an option for non-necrotising scleritis [S1]. Systemic corticosteroids are used when needed [S2]. Doses are not covered by these abstracts: follow local formularies.
- Treat the underlying disease with the rheumatology team [S5] [S9].
Tier C (specialist centre)
- Non-infectious necrotising scleritis requires aggressive combination immunosuppressive therapy [S11]. Timely immunosuppressive treatment reduces ocular and systemic morbidity [S1].
- Refractory disease: antimetabolites, calcineurin inhibitors, biologics and alkylating agents [S9]. Rituximab, usually as third-line or later, gave a positive response in 93.3% of 120 scleritis cases in a pooled case review (mostly GPA, 62.0%); no side effects were reported in 85.5% of scleritis cases [S7]. The most used regimen was two infusions of 1 g separated by 14 days (as reported in [S7]).
- Infectious scleritis needs long-term antimicrobials and often surgical debridement, drainage and patch grafting [S11]. Syphilitic scleritis usually responds to antibiotics rapidly, often within 1 week; almost one-quarter of reported patients had HIV co-infection [S12].
Refer when
| Situation | Urgency |
|---|---|
| Suspected necrotising or infectious scleritis, or scleritis after eye surgery | Same-day to an eye specialist [G1] [S11] |
| Suspected scleritis without necrosis | Urgent to an eye clinic; timing per your local service or specialist advice [S1] |
Pitfalls
- Giving corticosteroids for infectious scleritis [S6].
- Missing syphilis; initial misdiagnosis delayed antibiotics in reported cases [S12].
- Treating scleritis as an eye-only disease; it can precede systemic vasculitis [S5].
- Confusing episcleritis with scleritis [S3].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2012 | Narrative review |
| [S2] | 2013 | Narrative review (expert opinion) |
| [S3] | 2016 | Narrative review |
| [S4] | 2018 | Case report and literature review |
| [S5] | 2020 | Narrative review |
| [S6] | 2020 | Narrative review (India) |
| [S7] | 2021 | Review of published cases, 121 scleritis patients |
| [S8] | 2021 | Narrative review |
| [S9] | 2022 | Narrative review |
| [S10] | 2023 | Narrative review, GPA |
| [S11] | 2024 | Narrative review (India) |
| [S12] | 2024 | Review of 44 published patients |
- Thin evidence. All sources are reviews or case-based syntheses; most therapeutic decisions rest on observational data, and RCTs are lacking [S5].
- The rituximab figures pool published case data without a control group [S7].
- Not covered by these sources: NSAID and steroid doses, scleral imaging with ultrasound in low-resource settings, and outcomes by subtype.
Related articles
- Anterior Uveitis
- The red eye: triage
- Idiopathic Orbital Inflammation and IgG4-Related Orbital Disease
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Sims J Scleritis: presentations, disease associations and management. Postgraduate medical journal. (2012). PubMed 22977282 · doi:10.1136/postgradmedj-2011-130282
- [S2] Beardsley RM, Suhler EB, Rosenbaum JT, Lin P Pharmacotherapy of scleritis: current paradigms and future directions. Expert opinion on pharmacotherapy. (2013). PubMed 23425055 · doi:10.1517/14656566.2013.772982
- [S3] Daniel Diaz J, Sobol EK, Gritz DC Treatment and management of scleral disorders. Survey of ophthalmology. (2016). PubMed 27318032 · doi:10.1016/j.survophthal.2016.06.002
- [S4] Guerrero-Wooley RL, Peacock JE Infectious Scleritis: What the ID Clinician Should Know. Open forum infectious diseases. (2018). PubMed 29977974 · doi:10.1093/ofid/ofy140
- [S5] Nevares A, Raut R, Libman B, Hajj-Ali R Noninfectious Autoimmune Scleritis: Recognition, Systemic Associations, and Therapy. Current rheumatology reports. (2020). PubMed 32219644 · doi:10.1007/s11926-020-0885-y
- [S6] Murthy SI, Sabhapandit S, Balamurugan S, Subramaniam P, Sainz-de-la-Maza M, Agarwal M, et al. Scleritis: Differentiating infectious from non-infectious entities. Indian journal of ophthalmology. (2020). PubMed 32823398 · doi:10.4103/ijo.ijo_2032_20
- [S7] Ng CC, Sy A, Cunningham ET Rituximab for non-infectious Uveitis and Scleritis. Journal of ophthalmic inflammation and infection. (2021). PubMed 34396463 · doi:10.1186/s12348-021-00252-4
- [S8] Vermeirsch S, Testi I, Pavesio C Choroidal involvement in non-infectious posterior scleritis. Journal of ophthalmic inflammation and infection. (2021). PubMed 34705127 · doi:10.1186/s12348-021-00269-9
- [S9] Abdel-Aty A, Gupta A, Del Priore L, Kombo N Management of noninfectious scleritis. Therapeutic advances in ophthalmology. (2022). PubMed 35083421 · doi:10.1177/25158414211070879
- [S10] Mei L, Wang L, Yan H Updates of ocular involvement in granulomatosis with polyangiitis. Graefe's archive for clinical and experimental ophthalmology = Albrecht von Graefes Archiv fur klinische und experimentelle Ophthalmologie. (2023). PubMed 36473987 · doi:10.1007/s00417-022-05918-w
- [S11] Dutta Majumder P, Agarwal S, Shah M, Srinivasan B, K P, Iyer G, et al. Necrotizing Scleritis: A Review. Ocular immunology and inflammation. (2024). PubMed 37279404 · doi:10.1080/09273948.2023.2206898
- [S12] Shields MK, Furtado JM, Lake SR, Smith JR Syphilitic scleritis and episcleritis: A review. Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2024). PubMed 38795870 · doi:10.1016/j.apjo.2024.100073
Guidelines
- [G1] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 4.3 Scleritis (2026). https://www.eyes.nhs.scot/eyecare-guidelines/section-4-scleraepisclera/43-scleritis/