Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Smartphone and portable fundus imaging
Smartphone-based and handheld fundus cameras are portable, low-cost and easy to use in remote places, and images can be sent at once for remote grading [S2]. They can support screening or triage for referable diabetic retinopathy (DR), glaucoma-related disc changes and selected retinopathy of prematurity applications, with accuracy that varies by device, protocol, operator and disease [S11]. Combined with artificial intelligence (AI) and task-shifting, they are a practical route to eye screening in low-resource settings [S9].
Key points - Smartphone ophthalmoscopy detected any DR with pooled sensitivity 87% and specificity 94%, and proliferative DR with 92% and 99%, but mild non-proliferative DR with only 39% sensitivity [S1]. - Smartphone-based AI detected referable DR with pooled sensitivity 98.2% and specificity 81.2% in 6 studies (3,931 patients), four using one algorithm [S7]. - In developing countries, AI-based DR screening had pooled sensitivity 0.933 and specificity 0.903 for referable DR; portable cameras and general physicians agreed well with gold standards [S9]. - In Uganda, a smartphone adapter detected a vertical cup-to-disc ratio above 0.5 with 67.7% sensitivity and 96.7% specificity against OCT [S3]. - Image quality, field of view, data security, privacy, regulation and maintenance remain key challenges [S11].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags: findings on the image that need urgent action
- Proliferative DR on a screening image. Smartphone imaging detects it with the highest accuracy of any DR grade [S1]; refer within days [G1].
- Disc swelling in a neurology or emergency patient. In 79 neurology inpatients, 14.1% had neurologically relevant fundus pathology, including disc swelling, and routine direct ophthalmoscopy missed all of it [S5]; same-day assessment [EIC expert opinion].
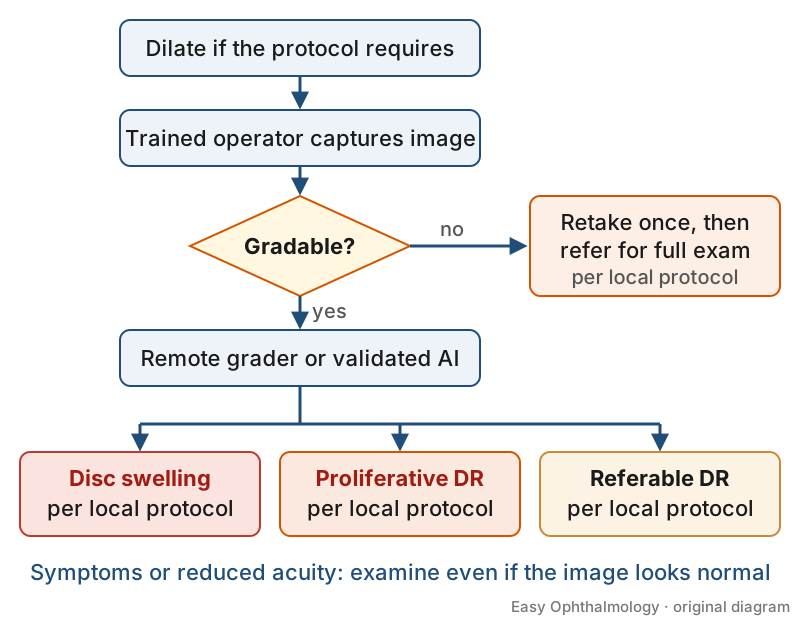
- An ungradable image. Not a normal result: re-image or refer, since dense cataract and poor acquisition cause image failure [S3].
- Suspected macular oedema. Smartphone sensitivity for DMO was 79% pooled [S1] and as low as 29.4% with some low-cost devices [S6], so symptoms or reduced acuity need examination even with a "normal" image.
Recognise it: device types and what they can do
- Smartphone-based fundus imaging (SBFI). A review of 30 hardware solutions in three main designs found some give fields of view and quality adequate for DR, disc and some ROP screening [S11].
- Digital ophthalmoscopes (smartphone, desktop, handheld): uptake is limited by image quality in undilated eyes, data confidence and lack of usage guidelines, but they are gaining acceptance in underserved areas [S8].
- Portable non-mydriatic fundus cameras. In neurology inpatients, portable non-mydriatic photography (sensitivity 45.5%) was more accurate than smartphone fundoscopy (30% to 40%), though the smartphone had fewer screening failures (1% vs 13%) and was quicker [S5].
- Teaching. Medical students identified abnormal discs more accurately with smartphone fundoscopy (74.4%) than with direct ophthalmoscopy (68.1%), and most preferred it [S4].
Confirm it: getting a gradable, reliable image
- Dilate when the protocol requires it. All low-cost smartphone devices in one review used mydriatic drops [S6], and image quality in non-mydriatic eyes is a concern [S8].
- Train the operator. After brief training, allied health workers can acquire usable images in selected settings [S11].
- Check gradability. In Uganda, 138 eyes were excluded for poor image acquisition such as dense cataract [S3].
- Know the reference standard. Reported accuracy depends on device, protocol, operator and reference standard; no universal performance threshold exists [S11].
Manage it: running a portable imaging programme at each tier
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Trained non-specialists can capture images for remote grading, supporting task-shifted screening and referral pathways [S9] [S11].
- Send images for remote grading by trained graders or ophthalmologists [S2], or use a validated AI system where available [S7] [S9].
- Refer every ungradable image or AI-positive result (see table).
Tier B (general eye clinic)
- Use portable cameras for documentation and patient counselling, as well as screening [S2].
- Use smartphone disc imaging to estimate cup-to-disc ratio in population screening; minimal training and low cost suit low-resource settings [S3].
- Use smartphone fundoscopy to teach and to support non-ophthalmic colleagues [S4] [S5].
Tier C (specialist centre)
- Act as the grading and referral hub for telemedicine programmes, which have widened screening coverage and timely referral of sight-threatening DR [S2].
- Audit programme accuracy locally: smartphone-based approaches are feasible but outcomes vary and need context-specific validation [S10].
- Address data governance, maintenance, regulatory compliance and photobiological safety when choosing devices [S11].
Refer when
| Situation | Urgency |
|---|---|
| Disc swelling on a portable image [S5] | Same-day [EIC expert opinion] |
| Proliferative DR on a screening image [S1] | Urgent; timing per your local service or specialist advice |
| Referable DR (graded or AI-positive) [S7] [S9] | Routine; timing per your local service or specialist advice [EIC expert opinion] |
| Ungradable image after one retake [S3] | Routine, for full examination; timing per your local service or specialist advice [EIC expert opinion] |
Pitfalls
- Treating an ungradable image as normal [S3].
- Relying on smartphone images to exclude mild DR or macular oedema [S1] [S6].
- Assuming all devices perform alike: camera type significantly affected accuracy [S9].
- Using undilated imaging where the protocol was validated with dilation [S6] [S8].
- Ignoring privacy and data security when sending images [S11].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2020 | Scoping review and meta-analysis, 9 studies, 1430 participants |
| [S2] | 2021 | Narrative review |
| [S3] | 2021 | Prospective diagnostic study, 467 patients, Uganda |
| [S4] | 2021 | Randomised crossover trial, 102 medical students |
| [S5] | 2022 | Prospective crossover diagnostic study, 79 inpatients |
| [S6] | 2023 | Systematic review, 5 studies |
| [S7] | 2023 | Systematic review and meta-analysis, 6 studies |
| [S8] | 2023 | Systematic review, 35 studies |
| [S9] | 2025 | Systematic review and meta-analysis, 25 studies, developing countries |
| [S10] | 2026 | Systematic review and meta-analysis, 45 studies |
| [S11] | 2026 | Scoping review, 30 devices, 274 publications |
- Pooled estimates are heterogeneous [S1]; four of six smartphone AI studies used one algorithm (Medios) [S7].
- The 2026 meta-analysis reported pooled odds ratios rather than sensitivity and specificity, and found possible publication bias for community screening [S10].
- Most evidence concerns DR; evidence for glaucoma and ROP is thinner [S3] [S11].
- Not covered by these sources: cost-effectiveness, named device comparisons, regulatory approval status by country and long-term programme outcomes.
Related articles
- Diabetic retinopathy screening programmes
- Artificial Intelligence in Retina and OCT
- Integrating eye care into primary health care
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Tan CH, Kyaw BM, Smith H, Tan CS, Tudor Car L Use of Smartphones to Detect Diabetic Retinopathy: Scoping Review and Meta-Analysis of Diagnostic Test Accuracy Studies. Journal of medical Internet research. (2020). PubMed 32347810 · doi:10.2196/16658
- [S2] Rajalakshmi R, Prathiba V, Arulmalar S, Usha M Review of retinal cameras for global coverage of diabetic retinopathy screening. Eye (London, England). (2021). PubMed 33168977 · doi:10.1038/s41433-020-01262-7
- [S3] Idriss BR, Tran TM, Atwine D, Chang RT, Myung D, Onyango J Smartphone-based Ophthalmic Imaging Compared With Spectral-domain Optical Coherence Tomography Assessment of Vertical Cup-to-disc Ratio Among Adults in Southwestern Uganda. Journal of glaucoma. (2021). PubMed 33394852 · doi:10.1097/ijg.0000000000001779
- [S4] Dunn HP, Marks S, Teo KZ, Dunn SM, Healey PR, White AJ eFOCUS 2: A randomised crossover trial of smartphone fundoscopy and direct ophthalmoscopy aiming to improve optic disc interpretation by medical students with e-learning support. Clinical & experimental ophthalmology. (2021). PubMed 34291862 · doi:10.1111/ceo.13977
- [S5] He G, Dunn HP, Ahmad KE, Watson E, Henderson A, Tynan D, et al. Fundoscopy use in neurology departments and the utility of smartphone photography: a prospective prevalence and crossover diagnostic accuracy study amongst neurology inpatients. European journal of neurology. (2022). PubMed 35531644 · doi:10.1111/ene.15390
- [S6] Prayogo ME, Zaharo AF, Damayanti NNR, Widyaputri F, Thobari JA, Susanti VY, et al. Accuracy of Low-Cost, Smartphone-Based Retinal Photography for Diabetic Retinopathy Screening: A Systematic Review. Clinical ophthalmology (Auckland, N.Z.). (2023). PubMed 37614846 · doi:10.2147/opth.s416422
- [S7] Hasan SU, Siddiqui MAR Diagnostic accuracy of smartphone-based artificial intelligence systems for detecting diabetic retinopathy: A systematic review and meta-analysis. Diabetes research and clinical practice. (2023). PubMed 37805002 · doi:10.1016/j.diabres.2023.110943
- [S8] Robles R, Patel N, Neag E, Mittal A, Markatia Z, Ameli K, et al. A Systematic Review of Digital Ophthalmoscopes in Medicine. Clinical ophthalmology (Auckland, N.Z.). (2023). PubMed 37822326 · doi:10.2147/opth.s423845
- [S9] Yudistira Y, Hendrawan KA, Andayani A, Suryathi NMA, Ernawati T, Gunawan ACV, et al. Diabetic Retinopathy Screening Approaches in Developing Countries: A Systematic Review and Meta-Analysis. Turkish journal of ophthalmology. (2025). PubMed 41142633 · doi:10.4274/tjo.galenos.2025.32916
- [S10] Wu Z, Li L Effectiveness of screening modalities for early detection of diabetic retinopathy: a systematic review and meta-analysis of tele-ophthalmology, AI-based tools, and conventional methods. Frontiers in medicine. (2026). PubMed 42100279 · doi:10.3389/fmed.2026.1778534
- [S11] Lechtenboehmer R, Cleland CR, Malerbi FK, Vaughan N, Rajalakshmi R, Young BK, et al. Smartphone-based fundus imaging in global eye care: Closing the gap. Progress in retinal and eye research. (2026). PubMed 42674180 · doi:10.1016/j.preteyeres.2026.101515
Guidelines
- [G1] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 10.3 Diabetic Retinopathy, Proliferative (n.d.). https://www.eyes.nhs.scot/eyecare-guidelines/section-10-retina/103-diabetic-retinopathy-proliferative/