Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Fluorescein and indocyanine green angiography
Fluorescein angiography (FA) and indocyanine green angiography (ICGA) are dye-based tests that show retinal and choroidal circulation; they remain part of multimodal imaging for macular neovascularisation alongside OCT and OCT angiography [S8]. FA is usually safe, but severe reactions occur in 0.04% to 0.59% of patients and deaths in 1 in 100,000 to 1 in 220,000 [S2]. Newer non-dye methods now replace angiography for some diagnoses [S4] [S5].
Key points - The only proven way to reduce FA reactions is to take an allergy history, specifically of a previous fluorescein reaction [S2]. - Dose, concentration, injection speed and temperature were not correlated with reaction rates [S2]. - Oral fluorescein angiography in children is a better-tolerated alternative to intravenous FA with good diagnostic images [S10]. - OCT angiography detects CNV in AMD with pooled sensitivity 0.89 and specificity 0.96, using FA as reference in most studies [S5]; polypoidal choroidal vasculopathy (PCV) can be diagnosed from OCT criteria where ICGA is not routine [S4]. - Wide-field FA detects more peripheral abnormalities in sickle cell retinopathy and ROP, though it may not change management for most sickle cell patients [S3] [S7].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags: findings during the test that need urgent action
- Signs of a severe reaction (breathing difficulty, collapse, widespread urticaria) after dye injection. Severe reactions occur in 0.04% to 0.59% [S2]; stop the test and start emergency management, following your national protocol [EIC expert opinion].
- A previous reaction to fluorescein. The only patient factor linked to a higher reaction rate [S2].
- Leakage from new vessels on FA in diabetic or sickle retinopathy. Peripheral neovascularisation may progress to vitreous haemorrhage or retinal detachment [S3]; refer to retina.
- ROP features seen only on FA after anti-VEGF treatment. Anti-VEGF treatment carries late-onset vision-threatening sequelae, and FA shows many features better than ophthalmoscopy [S7].
Recognise it: when angiography adds value
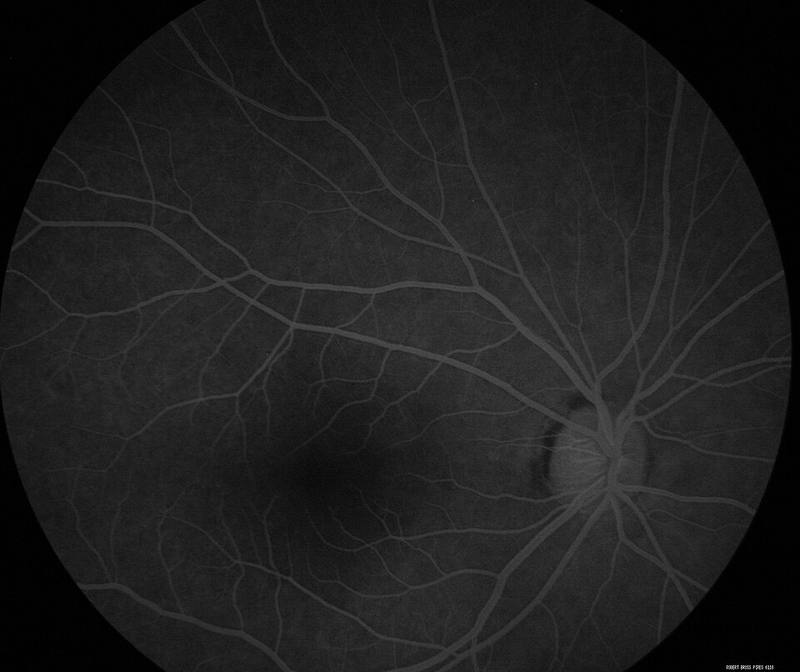
- Macular neovascularisation. Diagnosis uses multimodal imaging: OCT, OCT angiography, dye-based angiographies, autofluorescence and multiwavelength photography [S8]. The 2025 Japanese guideline defines neovascular AMD by MNV on multimodal imaging including OCT and OCTA, and disease activity by OCT [S11].
- PCV. A common subtype of neovascular AMD, more prevalent in Asian populations [S9]. Three OCT major criteria (sub-RPE ring-like lesion, en face complex RPE elevation, sharp-peaked PED) gave an AUC of 0.90 and 82% accuracy on validation [S4]. Non-ICGA OCTA features have been validated for diagnosis and monitoring [S9].
- Retinopathy of prematurity. Ultra-wide-field FA improves peripheral views; hand-held imaging can avoid anaesthesia [S7].
- Sickle cell retinopathy. Wide-field imaging captures up to 200 degrees and detects more microvascular abnormalities [S3].
Confirm it: running the test safely
- Before injection: ask about previous fluorescein reaction [S2].
- Diabetes and metformin: contrast-induced nephropathy has not been reported with fluorescein, and one review concludes it is unnecessary to stop metformin before FA [S1].
- Pregnancy: a survey found 24% of retina specialists withheld ICGA in pregnancy, mostly from fear of teratogenicity or lawsuit [S6]. Human studies found ICG undetectable in cord blood, and placental transfer is minimal [S6]. Fluorescein in pregnancy is not covered by these sources.
- Children: oral fluorescein at 25 mg/kg of 10% dye was the most common protocol, as reported in [S10]; mild reactions such as itching or nausea occurred in 0.019% [S10]. Intravenous dosing is not covered by these sources: follow local protocols.
Manage it: doing and acting on the test at each resource tier
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
FA is not performed at this level. Refer patients with suspected neovascularisation or unexplained vision loss (see table).
Tier B (general eye clinic)
- If performing FA, take an allergy history and record any previous fluorescein reaction [S2].
- Have emergency drugs and trained staff available during injection, following your national protocol [EIC expert opinion].
- Where OCT or OCTA is available, consider whether a non-dye test answers the question first [S5] [S8].
Tier C (specialist centre)
- Use FA, ICGA and OCTA within multimodal imaging for MNV [S8] [S11].
- For PCV, use ICGA where available; otherwise apply the validated OCT criteria [S4] [S9].
- Use wide-field FA selectively in sickle cell retinopathy after weighing risks and benefits [S3], and in ROP follow-up after anti-VEGF [S7].
- Consider oral fluorescein in children to avoid intravenous access [S10].
Refer when
| Situation | Urgency |
|---|---|
| Severe reaction during FA | Medical emergency: follow your national protocol [EIC expert opinion] |
| Suspected MNV with recent vision loss or distortion [S8] | Urgent to retina; timing per your local service or specialist advice |
| Retinal neovascularisation on FA (diabetes, sickle cell) [S3] | Urgent to retina; timing per your local service or specialist advice |
| Treated ROP with new findings on FA [S7] | Urgent to paediatric retina; timing per your local service or specialist advice |
Pitfalls
- Stopping metformin unnecessarily before FA [S1].
- Believing slow injection or dilution prevents reactions [S2].
- Withholding needed ICGA in pregnancy without considering the evidence [S6].
- Ordering FA when a validated non-dye test would answer the question [S4] [S5].
- Over-ordering wide-field FA where it may not change management [S3].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2017 | Narrative review |
| [S2] | 2019 | Literature review, 78 articles |
| [S3] | 2019 | Narrative review |
| [S4] | 2021 | Expert consensus with validation, 80 eyes |
| [S5] | 2021 | Systematic review and meta-analysis, 7 studies, 517 eyes |
| [S6] | 2022 | Systematic review |
| [S7] | 2023 | Narrative review |
| [S8] | 2025 | Narrative review |
| [S9] | 2025 | Expert consensus and guideline (APVRS) |
| [S10] | 2025 | Systematic review, 15 studies, 464 patients |
| [S11] | 2025 | National practice guideline (Japan) |
- Reaction rates come from heterogeneous studies spanning 1961 to 2017 [S2].
- The metformin conclusion is an expert opinion from one review [S1].
- The search returned off-topic records (ICG in surgery, anti-VEGF trials).
- Not covered by these sources: intravenous fluorescein and ICG doses, angiographic phases and interpretation of leakage, staining and pooling, iodine allergy and ICG, breastfeeding, and treatment protocols for reactions.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Du J, Li R Can Fundus Fluorescein Angiography be Performed for Diabetic Patients on Oral Metformin? Chinese medical sciences journal = Chung-kuo i hsueh k'o hsueh tsa chih. (2017). PubMed 28693693 · doi:10.24920/j1001-9294.2017.015
- [S2] Kornblau IS, El-Annan JF Adverse reactions to fluorescein angiography: A comprehensive review of the literature. Survey of ophthalmology. (2019). PubMed 30772364 · doi:10.1016/j.survophthal.2019.02.004
- [S3] Linz MO, Scott AW Wide-field imaging of sickle retinopathy. International journal of retina and vitreous. (2019). PubMed 31890287 · doi:10.1186/s40942-019-0177-8
- [S4] Cheung CMG, Lai TYY, Teo K, Ruamviboonsuk P, Chen SJ, Kim JE, et al. Polypoidal Choroidal Vasculopathy: Consensus Nomenclature and Non-Indocyanine Green Angiograph Diagnostic Criteria from the Asia-Pacific Ocular Imaging Society PCV Workgroup. Ophthalmology. (2021). PubMed 32795496 · doi:10.1016/j.ophtha.2020.08.006
- [S5] Chen CX, Liu ML, Cao K, Yusufu M, Wang JD Diagnostic Value of Optical Coherence Tomography Angiography for Choroidal Neovascularization in Age-Related Macular Degeneration: A Systematic Review and Meta-Analysis. Ophthalmic research. (2021). PubMed 33342974 · doi:10.1159/000511265
- [S6] Wang X, Zhang Y, Yang H, Xu Y Maternal-fetal transfer of indocyanine green: a systematic review. The journal of maternal-fetal & neonatal medicine : the official journal of the European Association of Perinatal Medicine, the Federation of Asia and Oceania Perinatal Societies, the International Society of Perinatal Obstetricians. (2022). PubMed 34565270 · doi:10.1080/14767058.2021.1966410
- [S7] Kvopka M, Chan W, Lake SR, Durkin S, Taranath D Fundus fluorescein angiography imaging of retinopathy of prematurity in infants: A review. Survey of ophthalmology. (2023). PubMed 37211096 · doi:10.1016/j.survophthal.2023.05.004
- [S8] Sheth JU, Stewart MW, Narayanan R, Anantharaman G, Chandran K, Lai TYY, et al. Macular neovascularization. Survey of ophthalmology. (2025). PubMed 39222802 · doi:10.1016/j.survophthal.2024.08.003
- [S9] Ruamviboonsuk P, Ng DSC, Chaikitmongkol V, Chang A, Chen SJ, Chen Y, et al. Consensus and guidelines on diagnosis and management of polypoidal choroidal vasculopathy (PCV) from the Asia-Pacific Vitreo-retina Society (APVRS). Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2025). PubMed 39824255 · doi:10.1016/j.apjo.2025.100144
- [S10] Ghaleb R, Sallam AB, Grigorian F, Phillips PH, Elhusseiny AM Oral fluorescein angiography in pediatric ophthalmology. Survey of ophthalmology. (2025). PubMed 40089030 · doi:10.1016/j.survophthal.2025.03.005
- [S11] Iida T, Gomi F, Yasukawa T, Yamashiro K, Honda S, Maruko I, et al. Japanese clinical guidelines for neovascular age-related macular degeneration. Japanese journal of ophthalmology. (2025). PubMed 40658332 · doi:10.1007/s10384-025-01240-0