Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
OCT angiography
OCT angiography (OCTA) is a signal processing and scan acquisition approach that lets OCT devices show retinal and choroidal vessels down to capillary level without dye [S10]. Unlike dye-based angiography it avoids risks such as anaphylaxis [S11]. It detects choroidal neovascularisation (CNV) with high accuracy [S1] and is used in diabetic retinopathy, glaucoma, geographic atrophy and neuro-ophthalmology [S2] [S6] [S7] [S8], but artefacts are common and are its main clinical limitation [S3].
Key points - A meta-analysis of 16 studies (447 CNV eyes, 414 controls) found pooled sensitivity 0.87 and specificity 0.97 for detecting CNV [S1]. - Artefacts from eye motion, layer misidentification (segmentation), projection and low signal are the most common; recognising them is essential for correct diagnosis [S3]. - In diabetic retinopathy OCTA measures the foveal avascular zone, vessel density and neovascularisation; poor-quality scans are relatively frequent and re-imaging is often needed [S7]. - Conventional OCTA has a small field of view; widefield OCTA now reaches the mid-periphery and beyond [S10] [S11]. - In glaucoma, OCTA has good repeatability and can extend monitoring of advanced disease beyond the "floor effect" of structural OCT [S8].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags: findings that need urgent action
- A neovascular network on OCTA in a symptomatic eye. OCTA has high diagnostic value for CNV [S1]; confirm with structural OCT and refer for treatment [G1].
- Neovascularisation on widefield OCTA in diabetic retinopathy. OCTA can identify neovascularisation [S7]; refer to retina [G2].
- CNV in an eye with uveitis. Inflammatory CNV is the third leading cause of CNV and is hard to separate from other uveitic lesions; OCT and OCTA help early detection [S9].
- An "abnormal" OCTA on a poor-quality scan. Check for artefact before acting [S3].
Recognise it: what OCTA shows
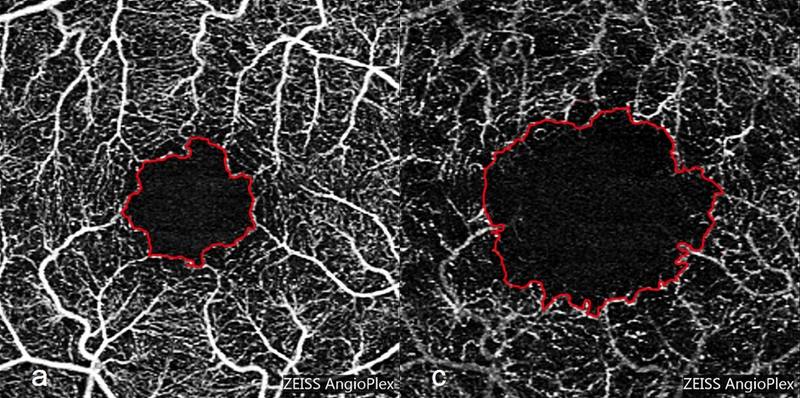
- Layers (slabs). OCTA visualises capillaries in all retinal layers in three dimensions [S7]; a full-retinal slab limits segmentation errors and confounding from centre-involved diabetic macular oedema [S7].
- Diabetic macular ischaemia. Traditionally graded by an enlarged, irregular foveal avascular zone, but these changes are not surrogate markers of visual impairment; OCTA perfusion nomenclature still needs standardising [S4].
- Geographic atrophy. Choriocapillaris flow changes are associated with GA development, extend beyond atrophy borders, are prognostic for progression and may help separate GA from mimics [S2].
- Neuro-ophthalmology. Peripapillary and macular OCTA may aid early detection and differential diagnosis, and the detection of complications in optic disc drusen [S6].
Confirm it: is the image real?
- Check scan quality. Proper scan quality evaluation is crucial for reliable metrics [S8].
- Look for artefacts: motion, segmentation errors, projection and low signal [S3].
- Device dependence. OCTA metrics vary with machine, post-processing algorithms, systemic disease and ocular factors [S8]; do not compare numbers across devices.
- Correlate with structural OCT and other imaging; combining modalities supports personalised care in diabetic retinopathy [S5].
Manage it: using OCTA at each resource tier
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
No OCTA role. Refer symptomatic macular disease according to the table below.
Tier B (general eye clinic)
- Where available, OCTA gives vascular imaging without dye risks such as anaphylaxis [S11].
- Use OCTA alongside colour photography, OCT and, when needed, fluorescein angiography to evaluate diabetic retinopathy [S5].
- Treat each OCTA finding as provisional until artefacts are excluded [S3].
Tier C (specialist centre)
- CNV diagnosis and follow-up. Use OCTA to detect CNV [S1] and to separate inflammatory CNV from other uveitic lesions [S9].
- Diabetic retinopathy. Use widefield OCTA, since peripheral vasculature matters for predicting progression [S7]. Allow time to re-image poor-quality scans [S7].
- Glaucoma. OCTA differentiates glaucomatous from healthy eyes and correlates with structural and field changes; it complements but does not replace standard tests [S8].
- Quantification and AI. Improved software and deep learning now allow precise quantification and automated diagnosis [S10]; clinical validation is still needed [S8].
Refer when
| Situation | Urgency |
|---|---|
| Suspected CNV on OCTA with symptoms or fluid [S1] | Urgent to retina; timing per your local service or specialist advice |
| Retinal neovascularisation on OCTA in diabetes [S7] | Urgent to retina; timing per your local service or specialist advice |
| OCTA unavailable but CNV suspected clinically | Urgent to a centre with OCT or angiography; timing per your local service or specialist advice |
| Abnormal perfusion only, no fluid or neovascularisation [S4] | Routine, review; timing per your local service or specialist advice |
Pitfalls
- Mistaking projection or segmentation artefacts for disease [S3].
- Comparing vessel density values between devices [S8].
- Missing peripheral disease on small-field scans [S11].
- Equating an enlarged foveal avascular zone with visual loss [S4].
- Overcalling glaucoma from OCTA metrics alone [S8].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2019 | Systematic review and meta-analysis, 16 studies |
| [S2] | 2021 | Narrative review |
| [S3] | 2021 | Narrative review |
| [S4] | 2022 | Narrative review |
| [S5] | 2022 | Narrative review |
| [S6] | 2023 | Narrative review |
| [S7] | 2023 | Expert narrative review |
| [S8] | 2024 | Narrative review of 272 original studies |
| [S9] | 2025 | Narrative review |
| [S10] | 2025 | Narrative review |
| [S11] | 2025 | Narrative review |
- Only one source is a meta-analysis [S1]; the others are narrative reviews, several by technology developers.
- Evidence on inflammatory CNV rests on case reports and series, with no RCTs [S9].
- Not covered by these sources: accuracy of OCTA versus fluorescein angiography for retinal neovascularisation, numeric normal values, cost, and use in low-resource settings.
Related articles
- OCT interpretation: macula and retinal nerve fibre layer
- Fluorescein and indocyanine green angiography
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Wang R, Liang Z, Liu X Diagnostic accuracy of optical coherence tomography angiography for choroidal neovascularization: a systematic review and meta-analysis. BMC ophthalmology. (2019). PubMed 31349806 · doi:10.1186/s12886-019-1163-5
- [S2] Müller PL, Pfau M, Schmitz-Valckenberg S, Fleckenstein M, Holz FG Optical Coherence Tomography-Angiography in Geographic Atrophy. Ophthalmologica. Journal international d'ophtalmologie. International journal of ophthalmology. Zeitschrift fur Augenheilkunde. (2021). PubMed 32772015 · doi:10.1159/000510727
- [S3] Anvari P, Ashrafkhorasani M, Habibi A, Falavarjani KG Artifacts in Optical Coherence Tomography Angiography. Journal of ophthalmic & vision research. (2021). PubMed 34055264 · doi:10.18502/jovr.v16i2.9091
- [S4] Cheung CMG, Fawzi A, Teo KY, Fukuyama H, Sen S, Tsai WS, et al. Diabetic macular ischaemia- a new therapeutic target? Progress in retinal and eye research. (2022). PubMed 34902545 · doi:10.1016/j.preteyeres.2021.101033
- [S5] Schreur V, Larsen MB, Sobrin L, Bhavsar AR, den Hollander AI, Klevering BJ, et al. Imaging diabetic retinal disease: clinical imaging requirements. Acta ophthalmologica. (2022). PubMed 35142031 · doi:10.1111/aos.15110
- [S6] Douglas VP, Douglas KAA, Torun N Optical coherence tomography angiography in neuro-ophthalmology. Current opinion in ophthalmology. (2023). PubMed 37070535 · doi:10.1097/icu.0000000000000955
- [S7] Waheed NK, Rosen RB, Jia Y, Munk MR, Huang D, Fawzi A, et al. Optical coherence tomography angiography in diabetic retinopathy. Progress in retinal and eye research. (2023). PubMed 37499857 · doi:10.1016/j.preteyeres.2023.101206
- [S8] Hong J, Tan SS, Chua J Optical coherence tomography angiography in glaucoma. Clinical & experimental optometry. (2024). PubMed 38266148 · doi:10.1080/08164622.2024.2306963
- [S9] Servillo A, Scandale P, Oldoni G, Begar PG, Bandello F, Miserocchi E, et al. Inflammatory choroidal neovascularization: An evidence-based update. Survey of ophthalmology. (2025). PubMed 39706532 · doi:10.1016/j.survophthal.2024.12.004
- [S10] Hormel TT, Huang D, Jia Y Advances in OCT Angiography. Translational vision science & technology. (2025). PubMed 40052848 · doi:10.1167/tvst.14.3.6
- [S11] Jia Y, Hormel TT, Hwang TS, Wu AL, Liang GB, Guo Y, et al. Widefield OCT angiography. Progress in retinal and eye research. (2025). PubMed 40517946 · doi:10.1016/j.preteyeres.2025.101378
Guidelines
- [G1] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 10.1 Age-Related Macular Degeneration- Neovascular (n.d.). https://www.eyes.nhs.scot/eyecare-guidelines/section-10-retina/101-age-related-macular-degeneration-neovascular/
- [G2] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 10.3 Diabetic Retinopathy, Proliferative (n.d.). https://www.eyes.nhs.scot/eyecare-guidelines/section-10-retina/103-diabetic-retinopathy-proliferative/