Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Non-Arteritic Anterior Ischaemic Optic Neuropathy
Non-arteritic anterior ischaemic optic neuropathy (NAION) is the most common acute optic neuropathy in people over 50 and a major cause of blindness in this age group [S6] [S10]. It presents with sudden, painless loss of vision with a swollen optic disc [S2] [S10]. No treatment has been proven effective [S2] [S6] [S10], so care focuses on accurate diagnosis, risk factors and protection of the fellow eye.
Key points - Typical presentation: sudden-onset, unilateral, painless loss of acuity and field, with pallid disc swelling [S2] [S10]. - Risk factors include male sex, hypertension, hyperlipidaemia, diabetes, coronary heart disease and sleep apnoea [S4]. - Optic nerve decompression surgery gave no benefit in the only RCT and caused serious complications [S2]. Neuroprotective and steroid treatments remain unproven [S3] [S6]. - Vision often worsens early: 91.6% of eyes that progressed did so by day 8 of the trial, within 22 days of onset [S9]. - GLP-1 receptor agonists, especially semaglutide, are associated with a small increase in NAION risk in mainly observational data; decisions about these drugs should be shared [S7] [S8] [S11].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Possible arteritic ischaemic optic neuropathy (giant cell arteritis) must be excluded urgently in anyone over 50 with optic disc swelling; see the giant cell arteritis article.
- Previous NAION in the fellow eye: the only consistent factor associated with progression of acuity and field loss [S9].
- Obstructive sleep apnoea, associated with progression [S9] and with NAION overall (risk ratio 3.28) [S4].
- Focal neurological signs or other atypical features: reconsider the diagnosis using history, examination and OCT [S10].
Recognise it
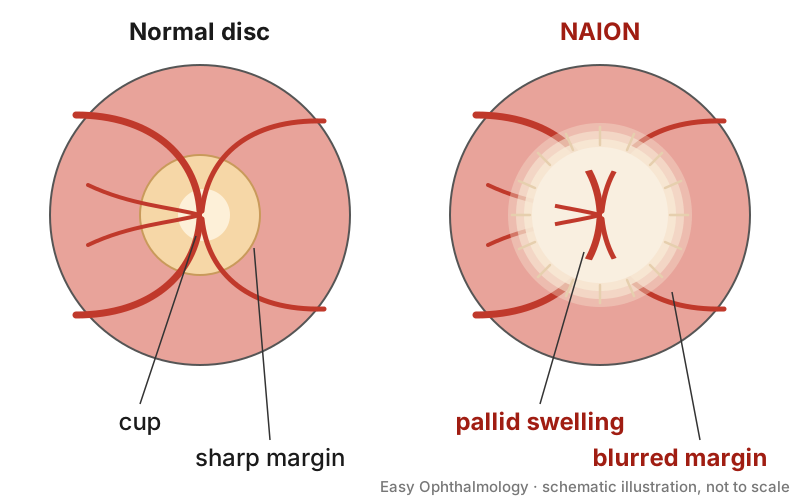
- Sudden, unilateral, painless visual loss with reduced acuity and field [S10].
- Risk factors (meta-analysis of 49 studies, more than 10 million patients): male sex (OR 1.67), hypertension (RR 1.28), hyperlipidaemia (RR 1.43), diabetes (RR 1.53), coronary heart disease (RR 1.68), sleep apnoea (RR 3.28) and factor V Leiden heterozygosity (RR 2.21) [S4].
- After cataract surgery: NAION risk is about four times higher within the first year (hazard ratio 4.6), mostly within 6 months, but absolute risk is low at 1 in 1,000 to 3,100 surgeries [S5].
- GLP-1 receptor agonists: a meta-analysis of 15 studies (more than 1.5 million patients) found odds ratio 1.70, with absolute risk 0.09% and number needed to harm about 2,700 [S8]. A semaglutide meta-analysis found hazard ratio 2.620, significant after 2 years of exposure [S7].
Confirm it
- Work-up includes history and examination with the relative afferent pupillary defect, visual fields and optical coherence tomography [S10].
- Use standardised acuity and automated perimetry to document a baseline; early progression is common [S9].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Refer sudden painless visual loss in one eye to an eye service (timing: see Refer when); NAION is a major cause of blindness over 50 [S10].
- Screen for and treat vascular risk factors and sleep apnoea, which are associated with NAION [S4]. Note that cardiovascular risk factors did not predict progression after onset [S9].
Tier B (general eye clinic)
- Confirm the diagnosis with pupils, fields and OCT [S10], and consider arteritic disease (see Red flags).
- Explain that there is no proven treatment [S2] [S10] and that vision may worsen over the first weeks: in trial sham eyes, 21.6% lost 10 letters or more by month 2 [S9].
- Steroids: evidence of benefit in ischaemic optic neuropathy is insufficient and patients often have comorbidities that increase steroid adverse events [S3]. One quasi-randomised trial (60 patients, Germany) reported better acuity with fluocortolone plus pentoxifylline than pentoxifylline alone, but no field benefit [S1]. Do not treat routinely on this basis.
- Do not refer for optic nerve decompression: in the only RCT (258 participants, stopped for futility), 29.4% vs 31.0% improved by 3 lines at 24 months, and surgery caused pain, diplopia and some cases of severe vision loss [S2].
- Patients on GLP-1 receptor agonists: the North American Neuro-Ophthalmology Society and American Academy of Ophthalmology (2026, expert consensus) advise shared decision-making on whether to start, continue or stop [S11].
Tier C (specialist centre)
- Neuroprotection: intravitreal QPI-1007 (725 participants, sham-controlled) did not meet its primary end point; a subgroup with baseline acuity 20/63 or worse lost less vision [S6]. This is investigational.
- Fellow-eye counselling: discuss risk factors such as sleep apnoea [S4] [S9] and, before cataract surgery in the fellow eye, the low absolute risk [S5].
Refer when
| Situation | Urgency |
|---|---|
| Sudden visual loss with disc swelling in a patient over 50 | Same-day, to exclude giant cell arteritis [EIC expert opinion] |
| Disc swelling with headache, jaw claudication or systemic symptoms | Immediate (see giant cell arteritis) |
| Confirmed NAION with worsening vision in the first weeks | Within days, to confirm the diagnosis [S9] |
| Confirmed NAION, stable | Routine review, with risk-factor management; timing per your local service or specialist advice [S4] |
Pitfalls
- Offering optic nerve decompression [S2].
- Overstating the GLP-1 risk: absolute risk is low and these drugs have mortality and cardio-kidney-metabolic benefits [S8] [S11].
- Assuming early worsening means a wrong diagnosis; progression usually occurs acutely [S9].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2014 | Quasi-randomised trial, 60 patients |
| [S2] | 2015 | Cochrane systematic review, 1 RCT |
| [S3] | 2018 | Narrative review |
| [S4] | 2021 | Meta-analysis of 49 observational studies, unadjusted |
| [S5] | 2023 | Systematic review and meta-analysis |
| [S6] | 2026 | Phase 2/3 sham-controlled RCT, 725 participants |
| [S7] | 2026 | Meta-analysis of 10 observational studies |
| [S8] | 2026 | Meta-analysis of 15 studies, including 8 trials |
| [S9] | 2026 | Secondary analysis of an RCT cohort |
| [S10] | 2026 | Narrative review |
| [S11] | 2026 | Expert consensus statement (NANOS/AAO) |
- Conflict: the fluocortolone trial claims benefit [S1], while a review finds steroid evidence insufficient [S3]; the trial was small and quasi-randomised.
- GLP-1 evidence is mainly retrospective claims and health-record data; some studies show no association [S11]. Pooled RCT data were not statistically significant (OR 2.36, 95% CI 0.85 to 6.53) [S8].
- Risk-factor odds ratios are unadjusted [S4].
- The red flag and referral advice on giant cell arteritis has no source in this sheet: the Editor-in-Chief should link it to the giant cell arteritis article.
- Not covered by these sources: aspirin, phosphodiesterase inhibitors, nocturnal hypotension, the risk to the fellow eye in figures, and data from low- and middle-income countries.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Prokosch V, Thanos S Visual outcome of patients following NAION after treatment with adjunctive fluocortolone. Restorative neurology and neuroscience. (2014). PubMed 24225379 · doi:10.3233/rnn-120292
- [S2] Dickersin K, Li T Surgery for nonarteritic anterior ischemic optic neuropathy. The Cochrane database of systematic reviews. (2015). PubMed 25763979 · doi:10.1002/14651858.cd001538.pub4
- [S3] Stunkel L, Van Stavern GP Steroid Treatment of Optic Neuropathies. Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2018). PubMed 29962119 · doi:10.22608/apo.2018127
- [S4] Liu B, Yu Y, Liu W, Deng T, Xiang D Risk Factors for Non-arteritic Anterior Ischemic Optic Neuropathy: A Large Scale Meta-Analysis. Frontiers in medicine. (2021). PubMed 34671609 · doi:10.3389/fmed.2021.618353
- [S5] Shew W, Wang MTM, Danesh-Meyer HV Nonarteritic Anterior Ischemic Optic Neuropathy After Cataract Surgery: A Systematic Review and Meta-Analysis. Journal of neuro-ophthalmology : the official journal of the North American Neuro-Ophthalmology Society. (2023). PubMed 36166807 · doi:10.1097/wno.0000000000001625
- [S6] Levin LA, Bhatti MT, Klier S, Morgenstern R, Szanto D, Miller NR, et al. A Randomized Sham-Controlled Phase 2/3 Trial of QPI-1007 for Acute Nonarteritic Anterior Ischemic Optic Neuropathy. Ophthalmology. (2026). PubMed 40816607 · doi:10.1016/j.ophtha.2025.07.039
- [S7] Chen KY, Chan HC, Chan CM Does semaglutide increase the risk of non-arteritic anterior ischemic optic neuropathy? A systematic review and meta-analysis of emerging evidence. Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2026). PubMed 40962119 · doi:10.1016/j.apjo.2025.100245
- [S8] Nogueira A, Rassi TNO, Iqbal A, Felix N, Alghaith O, Khan A, et al. Association Between GLP-1 Receptor Agonists and Ischemic Optic Neuropathy: A Meta-analysis. Diabetes care. (2026). PubMed 41498755 · doi:10.2337/dc25-1238
- [S9] Williams ZR, Morgenstern R, Erekat AN, Szanto D, Wall M, Miller NR, et al. Progression of Nonarteritic Anterior Ischemic Optic Neuropathy (NAION) Occurs Early and Is Unassociated With Modifiable Risk Factors. American journal of ophthalmology. (2026). PubMed 41544737 · doi:10.1016/j.ajo.2026.01.012
- [S10] Ababneh OH, Al-Asmar RK, Fashho ER, Qatawneh AT Nonarteritic Anterior Ischemic Optic Neuropathy: Review and Update. Neurologic clinics. (2026). PubMed 41922029 · doi:10.1016/j.ncl.2025.11.001
- [S11] DeParis SW, Oke I, Gaier ED, Moss HE, MacIntosh PW, Gilbert AL, et al. Glucagon-Like Peptide-1 Receptor Agonists and the Risk of Non-Arteritic Anterior Ischemic Optic Neuropathy: A Consensus Statement by the North American Neuro-Ophthalmology Society and the American Academy of Ophthalmology. Ophthalmology. (2026). PubMed 42132708 · doi:10.1016/j.ophtha.2026.04.008