Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Biologics and Immunosuppression for Non-infectious Uveitis
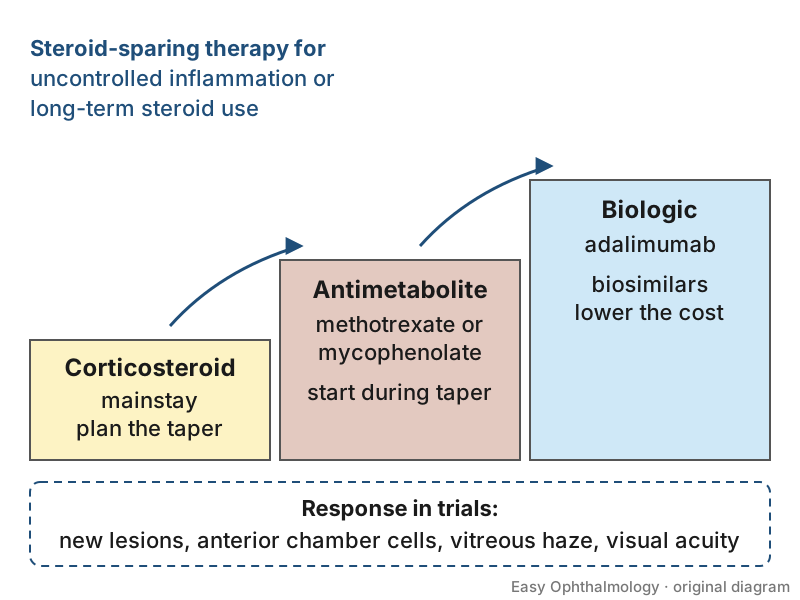
Non-infectious uveitis (NIU) is a chronic immune-mediated inflammation that may cause irreversible visual impairment [S12]. Corticosteroids are the mainstay of treatment [S4], but long-term use causes adverse effects, so steroid-sparing therapy with antimetabolites and biologics is used [S2] [S3]. Adalimumab has the most consistent randomised evidence; the choice between agents in practice is shaped by cost and access [S8] [S12].
Key points - Methotrexate and mycophenolate mofetil are both reasonable first-line steroid-sparing antimetabolites; in the FAST trial mycophenolate was not superior to methotrexate [S3]. - Adalimumab reduces treatment failure in active and corticosteroid-controlled intermediate, posterior and panuveitis, with more adverse events than placebo in VISUAL I [S1] [S2] [S12]. - Biosimilar adalimumab or infliximab was not associated with more flares after switching, which matters where cost limits access [S8] [S9]. - Corticosteroid implants may reduce recurrence but increase cataract and raised intraocular pressure (IOP); certainty is low to moderate [S4]. - Relapse risk remains despite immunomodulatory therapy [S10].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Infectious uveitis is a different disease. The trials here enrolled non-infectious uveitis only [S1] [S2] [S3]; their results do not apply to infectious uveitis.
- Persistent inflammation despite therapy. The estimated treatment failure rate at month 6 across trials was 37.6% [S10]; flares need review, not just more steroid.
- Steroid dependence. The Egyptian consensus recommends that maintenance prednisone should not exceed 7.5 mg daily (as reported in [S8]).
- Raised IOP and cataract after steroid implants [S4].
- Early flare after a biosimilar switch. A subset of patients flare early or have tolerability problems, so monitor closely in the months after switching [S9].
Recognise it: who needs steroid-sparing therapy
- Patients with uncontrolled inflammation risk long-term complications, and those on long-term glucocorticoids risk drug adverse effects [S2].
- The Egyptian consensus advises starting systemic immunosuppression during the steroid taper, and first-line together with steroids when there is underlying systemic disease [S8].
- The adalimumab trials enrolled adults with intermediate uveitis, posterior uveitis or panuveitis that was active despite prednisone for 2 or more weeks [S2], or inactive on 10-35 mg/day prednisone [S1].
Confirm it: measuring response
- Trials defined treatment failure as a composite of new inflammatory lesions, anterior chamber cell grade, vitreous haze grade and best-corrected visual acuity [S1] [S2].
- FAST defined success at 6 months as control of inflammation in both eyes on no more than 7.5 mg prednisone daily and no more than 2 drops of prednisolone acetate 1% (as reported in [S3]).
- Anti-adalimumab antibodies: pooled prevalence 9% and 12-month incidence 27%, higher in real-life studies than trials; not using a concomitant immunosuppressant was one associated factor [S6].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Do not start or stop systemic immunosuppression without the treating uveitis or rheumatology team; these drugs carry real adverse-event burdens [S2] [S3].
- Report new symptoms in patients on these drugs to the treating team; injection-site reactions are more common with adalimumab [S12], and liver enzyme rises occurred with methotrexate and mycophenolate [S3].
Tier B (general eye clinic)
- Steroids first, with a plan to taper. Corticosteroids are the mainstay of treatment [S4]; start a steroid-sparing agent during the taper [S8].
- Antimetabolites. In FAST (216 adults, centres in India, the USA, Australia, Saudi Arabia and Mexico), treatment success at 6 months was 66.7% with methotrexate 25 mg weekly vs 57.1% with mycophenolate mofetil 3 g daily (doses as reported in [S3]); the difference was not significant [S3]. In posterior uveitis or panuveitis methotrexate did better (74.4% vs 55.3%); in intermediate uveitis the trend favoured mycophenolate (33.3% vs 63.6%, not significant) [S3]. Elevated liver enzymes occurred in 13.0% and 7.4% respectively [S3].
- Comanage with rheumatology, particularly when systemic disease is present [S8].
- Before any biologic, screen for tuberculosis and hepatitis B according to local protocol [EIC expert opinion].
Tier C (specialist centre)
- Adalimumab. - VISUAL I (active NIU, 217 patients): median time to treatment failure 24 vs 13 weeks; hazard ratio 0.50; more adverse events and serious adverse events (28.8 vs 13.6 per 100 person-years) [S2]. Industry funded [S2]. - VISUAL II (inactive NIU on prednisone, 226 analysed): treatment failure in 39% vs 55%, hazard ratio 0.57; adverse event rates similar between groups [S1]. Industry funded [S1]. - Trial dosing was an 80 mg loading dose then 40 mg every 2 weeks (as reported in [S1] [S2]). - Pooled: adalimumab reduced treatment failure vs placebo (risk ratio 0.67) and increased injection-site reactions (risk ratio 2.67); the mortality estimate was inconclusive [S12]. Adalimumab plus corticosteroids prolonged the relapse-free period vs corticosteroids alone (hazard ratio 0.51) [S10].
- Tocilizumab and anakinra. In a French Bayesian RCT of 112 patients with active, refractory non-anterior NIU, the primary vitreous haze outcome at week 16 was reached in 16% with adalimumab and 14% with tocilizumab; anakinra was ineffective and its arm stopped early [S11].
- Infliximab. Comparative safety estimates are uncertain and hypothesis-generating [S12].
- Biosimilars. In 202 patients switched from originator TNF-α inhibitors, the flare rate ratio was 1.26 (not significant), with no change in oral steroid or non-biologic immunomodulator use; 10% reverted to the originator, mostly because of injection-site pain or injector problems [S9]. The Egyptian consensus emphasises biosimilars for their lower cost, and conventional immunosuppression is usually exhausted before biologics in that setting [S8].
- Corticosteroid implants (fluocinolone acetonide or dexamethasone). Cochrane (2023, 4 trials, 683 participants): vs sham, recurrence may fall by 60% at 6 months (low certainty); vs standard of care, recurrence likely falls by 54% at 24 months, with little or no difference in visual acuity [S4]. Implants increased raised IOP and the 0.59 mg fluocinolone implant increased cataract progression and surgery; endophthalmitis, retinal tear and detachment were not increased [S4].
Refer when
| Situation | Urgency |
|---|---|
| Patient on immunosuppression with a new red, painful eye or vision loss | Same-day eye review [G1] |
| Intermediate, posterior or panuveitis needing steroid-sparing therapy, or flaring despite an antimetabolite | Routine to a uveitis service comanaging with rheumatology; timing per your local service or specialist advice [S8] [S12] |
Pitfalls
- Assuming mycophenolate is better than methotrexate; FAST did not show this [S3].
- Ignoring anti-drug antibodies when adalimumab stops working; they are common in real-life practice [S6].
- Counting a single trial's adverse event rates as the full safety picture; long-term head-to-head data are lacking [S12].
- Overlooking cost: NIU costs are highest in patients with blindness and those on advanced therapies [S7].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2016 | Phase 3 RCT (VISUAL II), industry funded |
| [S2] | 2016 | Phase 3 RCT (VISUAL I), industry funded |
| [S3] | 2019 | RCT (FAST), multinational including India |
| [S4] | 2023 | Cochrane systematic review, 4 RCTs |
| [S5] | 2023 | Systematic review of guidelines (for WHO) |
| [S6] | 2024 | Meta-analysis, 9 studies |
| [S7] | 2025 | Systematic review of economic studies |
| [S8] | 2025 | National consensus (Egypt), expert opinion with literature review |
| [S9] | 2026 | Meta-analysis, 6 observational studies |
| [S10] | 2026 | Network meta-analysis, 16 RCTs |
| [S11] | 2026 | Bayesian RCT, 112 patients, France |
| [S12] | 2026 | Pairwise and network meta-analysis, 7 studies |
- A WHO-commissioned review found only 3 usable uveitis guidelines and many recommendations based on expert opinion [S5].
- The two meta-analyses differ: one found no significant differences between treatments in 6-month failure or visual acuity [S10], the other found adalimumab the most consistent agent [S12].
- Economic evidence comes mostly from the USA and UK; data from other countries are lacking [S7].
- Not covered by these sources: infection screening before biologics, vaccination, pregnancy, paediatric dosing, cyclosporine, tacrolimus, JAK inhibitors, and treatment duration before tapering.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Nguyen QD, Merrill PT, Jaffe GJ, Dick AD, Kurup SK, Sheppard J, et al. Adalimumab for prevention of uveitic flare in patients with inactive non-infectious uveitis controlled by corticosteroids (VISUAL II): a multicentre, double-masked, randomised, placebo-controlled phase 3 trial. Lancet (London, England). (2016). PubMed 27542302 · doi:10.1016/s0140-6736(16)31339-3
- [S2] Jaffe GJ, Dick AD, Brézin AP, Nguyen QD, Thorne JE, Kestelyn P, et al. Adalimumab in Patients with Active Noninfectious Uveitis. The New England journal of medicine. (2016). PubMed 27602665 · doi:10.1056/nejmoa1509852
- [S3] Rathinam SR, Gonzales JA, Thundikandy R, Kanakath A, Murugan SB, Vedhanayaki R, et al. Effect of Corticosteroid-Sparing Treatment With Mycophenolate Mofetil vs Methotrexate on Inflammation in Patients With Uveitis: A Randomized Clinical Trial. JAMA. (2019). PubMed 31503307 · doi:10.1001/jama.2019.12618
- [S4] Reddy A, Liu SH, Brady CJ, Sieving PC, Palestine AG Corticosteroid implants for chronic non-infectious uveitis. The Cochrane database of systematic reviews. (2023). PubMed 36645716 · doi:10.1002/14651858.cd010469.pub3
- [S5] Ghadiri N, Reekie IR, Gordon I, Safi S, Lingham G, Evans JR, et al. Systematic review of clinical practice guidelines for uveitis. BMJ open ophthalmology. (2023). PubMed 37278434 · doi:10.1136/bmjophth-2022-001091
- [S6] Pachón-Suárez DI, Zárate-Pinzón L, Cifuentes-González C, Rojas-Carabali W, Mejía-Salgado G, Pineda JS, et al. Immunogenicity of Adalimumab in Patients with Non-Infectious Uveitis: Systematic Review and Meta-Analysis. Ocular immunology and inflammation. (2024). PubMed 37796609 · doi:10.1080/09273948.2023.2256850
- [S7] Sriranganathan A, Mihalache A, Grad J, Miranda RN, Felfeli T Economic Burden and Cost-Effectiveness of Management of Non-Infectious Uveitis: A Systematic Review. Ocular immunology and inflammation. (2025). PubMed 39773098 · doi:10.1080/09273948.2025.2450472
- [S8] El-Ghobashy N, El-Garf A, Mohamed Youssef M, El Nokrashy A, Ashour DM, Aboul Naga SH, et al. Egyptian Consensus Guidance for Treatment of Adults with Non-Infectious Uveitis. Ocular immunology and inflammation. (2025). PubMed 40314690 · doi:10.1080/09273948.2025.2493362
- [S9] Zhang C, Ayoubi M, Aboukasm G, Ersan S, Zhu D, Wong A, et al. Clinical Efficacy of Biosimilar Switch of Adalimumab and Infliximab for Noninfectious Uveitis: Systematic Review and Meta-Analysis. American journal of ophthalmology. (2026). PubMed 41265720 · doi:10.1016/j.ajo.2025.11.015
- [S10] Wang J, Zhong Z, Zhang P, Weng W, Yang P Comparative Effects of Immunomodulatory Therapies in Non-Infectious Uveitis: A Systematic Review and Meta-Analysis. Ocular immunology and inflammation. (2026). PubMed 41412963 · doi:10.1080/09273948.2025.2599370
- [S11] Saadoun D, Ghembaza A, Touhami S, Girszyn N, Bielefeld P, Seve P, et al. Adalimumab, Anakinra, and Tocilizumab in Patients With Noninfectious Uveitis: A Multicenter Randomized Controlled Trial. American journal of ophthalmology. (2026). PubMed 41643758 · doi:10.1016/j.ajo.2026.01.037
- [S12] Chen KY, Chan HC, Chan CM Comparative Efficacy and Safety of Systemic Immunomodulatory Therapies for Non-Infectious Uveitis: A Systematic Review With Pairwise and Network Meta-Analyses. Pharmacotherapy. (2026). PubMed 42870312 · doi:10.1002/phar.70184
Guidelines
- [G1] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 7.1 Acute Anterior Uveitis (2025). https://www.eyes.nhs.scot/eyecare-guidelines/section-7-uvea/71-acute-anterior-uveitis/