Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
OCT interpretation: macula and retinal nerve fibre layer
Optical coherence tomography (OCT) gives cross-sectional images of the macula, retinal nerve fibre layer (RNFL), ganglion cell layer and optic nerve head [S8]. It is central to diagnosing and monitoring macular disease [S10] [S11] and glaucoma [S4] [S7], but reliable reading needs standard terminology [S1], high-quality scans that are actually looked at [S2], and awareness of normative database limits [S3] [S5].
Key points - Read the scan, not just the colour map: visual analysis of a high-quality circle scan helps avoid both false positive and false negative glaucoma calls [S2]. - Average RNFL thickness was the most accurate single Stratus OCT parameter for glaucoma, but accuracy was lower in Asian populations [S3]. - Macular OCT is reproducible and supports detection of early glaucoma [S7]; confirm any apparent progression on at least one repeat scan after two or more baseline scans [S4]. - No commercial OCT device includes a paediatric normative database, which can lead to important interpretation errors in children [S5]. - Macular neovascularisation, diabetic macular oedema and disc swelling are best assessed with multimodal imaging, of which OCT is one part [S8] [S10] [S11].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags: findings that need urgent action
- New subretinal or intraretinal fluid with a grey-green macular lesion or symptoms of distortion. Suggests macular neovascularisation [S11]; needs prompt retina assessment [G1].
- Retinal thickening involving the fovea in diabetes. Diabetic macular oedema can cause vision impairment and blindness [S10].
- Peripapillary wrinkles or outer retinal creases on en face OCT. Common, distinctive signs of optic disc oedema that rule out pseudopapilledema [S8]; same-day systemic or neurological assessment [EIC expert opinion].
- Superonasal RNFL thinning with a field defect. More typical of anterior ischaemic optic neuropathy than glaucoma [S9].
Recognise it: reading the macular scan
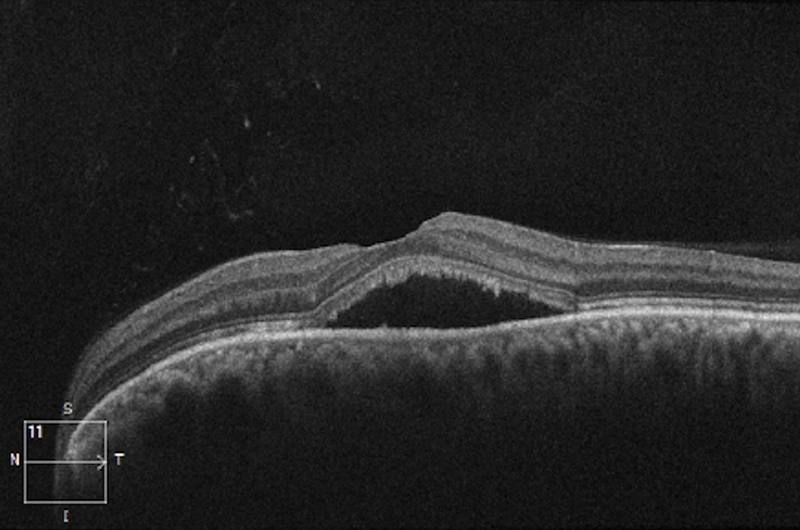
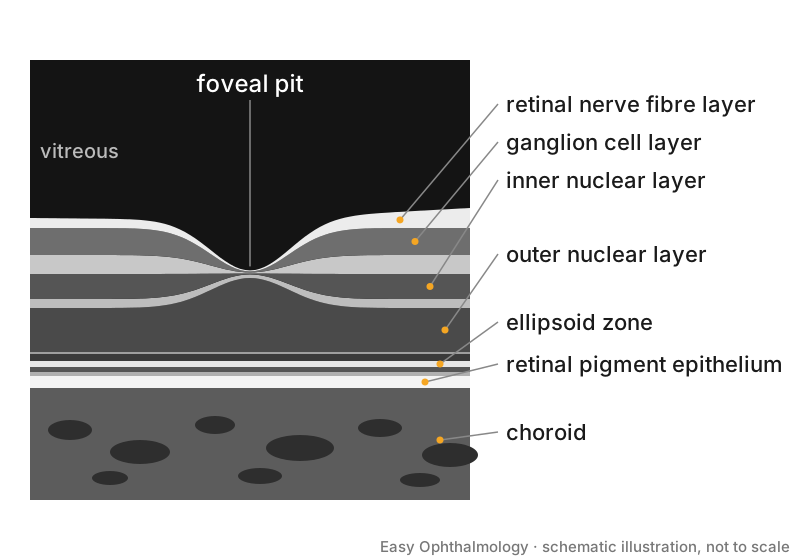
- Layers. Use the IN•OCT consensus terms for normal bands, including the ellipsoid and interdigitation zones [S1].
- Macular neovascularisation (MNV). The CONAN term covers intraretinal, subretinal and sub-RPE neovascularisation; MNV often shows intraretinal thickening and/or subretinal exudation [S11].
- Diabetic macular oedema. Retinal thickening near or involving the fovea from fluid accumulation [S10].
- Lamellar macular hole (LMH) and mimics [S6]:
| Entity | Mandatory OCT criteria [S6] |
|---|---|
| Lamellar macular hole | Irregular foveal contour; foveal cavity with undermined edges; apparent loss of foveal tissue |
| ERM foveoschisis | Epiretinal membrane; schisis at Henle's fibre layer |
| Macular pseudohole | Foveal-sparing ERM; steepened foveal profile; increased central retinal thickness |
Confirm it: reading the RNFL and optic nerve scan
- Check quality and artefacts. Inspect the circle scan itself [S2]; recognise common artefacts and optimise acquisition [S8].
- Match structure and function. Compare the location of abnormal field points with regions of abnormal ganglion cell and RNFL thickness [S2].
- Sector pattern. In a systematic review of 39 studies, glaucoma thinned mainly superotemporal, inferotemporal and inferonasal RNFL, while AION mostly thinned superonasal RNFL; glaucoma also showed larger cups and thinner Bruch's membrane opening-minimum rim width [S9].
- Disc swelling. RNFL and GC-IPL thickness have limits when swelling is severe; SD-OCT is the most sensitive way to identify buried disc drusen [S8].
- Children. Use published paediatric normative data, not the device's adult database [S5].
Manage it: using OCT at each resource tier
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
OCT interpretation is a Tier B / Tier C skill. Where an OCT report reaches primary care, act on it using the Refer when table below.
Tier B (general eye clinic)
- Combine OCT with fundus examination and other imaging for DME and MNV [S10] [S11].
- Do not label glaucoma on the colour map alone; review scan quality and correlate with the field [S2].
- Take extra care with normative comparisons in Asian patients [S3] and children [S5].
Tier C (specialist centre)
- Glaucoma progression. A RNFL loss slope greater than -1 per year is associated with a higher risk of future field loss, and ganglion cell complex change is often earlier than RNFL change [S4]. Use two or more baseline scans and confirm change on a repeat scan [S4].
- Neuro-ophthalmology. Use transverse axial, en face and circular tomograms qualitatively, and adduction scans in papilledema, to expose folds [S8].
- Macular disease. Use OCT within multimodal imaging (OCT angiography, dye angiography, autofluorescence, wide-field photography) to diagnose and guide treatment [S10] [S11].
- Use standard nomenclature in reports and research [S1] [S6].
Refer when
| Situation | Urgency |
|---|---|
| New macular fluid or suspected MNV [S11] | Urgent to retina; timing per your local service or specialist advice |
| Signs of optic disc oedema on OCT [S8] | Same-day [EIC expert opinion] |
| DME involving the fovea [S10] | Within a few weeks to retina [EIC expert opinion] |
| Confirmed glaucomatous RNFL or GCC progression [S4] | Routine to glaucoma service; timing per your local service or specialist advice |
Pitfalls
- Trusting colour-coded probability maps without inspecting the scan [S2].
- Using adult normative data in children [S5].
- Calling progression from one follow-up scan [S4].
- Confusing pseudohole or ERM foveoschisis with lamellar hole [S6].
- Assuming RNFL thinning means glaucoma when the pattern fits AION [S9].
- Relying on RNFL thickness when disc swelling is severe [S8].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2014 | International consensus (nomenclature) |
| [S2] | 2014 | Narrative review with case analysis |
| [S3] | 2014 | Meta-analysis (Stratus OCT) |
| [S4] | 2019 | Narrative review |
| [S5] | 2019 | Narrative review |
| [S6] | 2020 | Expert consensus |
| [S7] | 2020 | Narrative review |
| [S8] | 2021 | Narrative review |
| [S9] | 2024 | Systematic review, 39 studies |
| [S10] | 2024 | Narrative review |
| [S11] | 2025 | Narrative review |
- The meta-analysis used an older time-domain device (Stratus) [S3]; accuracy of modern devices is not covered by these sources.
- The paediatric normative review focuses on Spanish and European populations [S5].
- Most sources are narrative reviews or consensus statements; one systematic review [S9] and one meta-analysis [S3] are included.
- The search returned many off-topic records (coronary and skin OCT, psychiatric and neurological biomarkers).
- Not covered by these sources: specific thickness cut-offs for DME, scan protocols by device, segmentation error rates, and accuracy data for modern spectral-domain glaucoma parameters.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Staurenghi G, Sadda S, Chakravarthy U, Spaide RF, International Nomenclature for Optical Coherence Tomography (IN•OCT) Panel Proposed lexicon for anatomic landmarks in normal posterior segment spectral-domain optical coherence tomography: the IN•OCT consensus. Ophthalmology. (2014). PubMed 24755005 · doi:10.1016/j.ophtha.2014.02.023
- [S2] Hood DC, Raza AS On improving the use of OCT imaging for detecting glaucomatous damage. The British journal of ophthalmology. (2014). PubMed 24934219 · doi:10.1136/bjophthalmol-2014-305156
- [S3] Chen HY, Chang YC Meta-analysis of stratus OCT glaucoma diagnostic accuracy. Optometry and vision science : official publication of the American Academy of Optometry. (2014). PubMed 25036543 · doi:10.1097/opx.0000000000000331
- [S4] Renard JP, Fénolland JR, Giraud JM Glaucoma progression analysis by Spectral-Domain Optical Coherence Tomography (SD-OCT). Journal francais d'ophtalmologie. (2019). PubMed 30955899 · doi:10.1016/j.jfo.2019.03.001
- [S5] Muñoz-Gallego A, Rodríguez-Salgado M, de la Cruz J, López-López C, Cañas-Zamarra I, Tejada-Palacios P Paediatric optical coherence tomography normative databases: A real need. Archivos de la Sociedad Espanola de Oftalmologia. (2019). PubMed 31685301 · doi:10.1016/j.oftal.2019.08.003
- [S6] Hubschman JP, Govetto A, Spaide RF, Schumann R, Steel D, Figueroa MS, et al. Optical coherence tomography-based consensus definition for lamellar macular hole. The British journal of ophthalmology. (2020). PubMed 32107208 · doi:10.1136/bjophthalmol-2019-315432
- [S7] Mohammadzadeh V, Fatehi N, Yarmohammadi A, Lee JW, Sharifipour F, Daneshvar R, et al. Macular imaging with optical coherence tomography in glaucoma. Survey of ophthalmology. (2020). PubMed 32199939 · doi:10.1016/j.survophthal.2020.03.002
- [S8] Sibony PA, Kupersmith MJ, Kardon RH Optical Coherence Tomography Neuro-Toolbox for the Diagnosis and Management of Papilledema, Optic Disc Edema, and Pseudopapilledema. Journal of neuro-ophthalmology : the official journal of the North American Neuro-Ophthalmology Society. (2021). PubMed 32909979 · doi:10.1097/wno.0000000000001078
- [S9] Smeets F, Margot A, Barbosa-Breda J, Stalmans I, Lemmens S Differentiating Ischemic Optic Neuropathy from Glaucoma Using Diagnostic Tests. Ophthalmic research. (2024). PubMed 38262372 · doi:10.1159/000535568
- [S10] Parravano M, Cennamo G, Di Antonio L, Grassi MO, Lupidi M, Rispoli M, et al. Multimodal imaging in diabetic retinopathy and macular edema: An update about biomarkers. Survey of ophthalmology. (2024). PubMed 38942124 · doi:10.1016/j.survophthal.2024.06.006
- [S11] Sheth JU, Stewart MW, Narayanan R, Anantharaman G, Chandran K, Lai TYY, et al. Macular neovascularization. Survey of ophthalmology. (2025). PubMed 39222802 · doi:10.1016/j.survophthal.2024.08.003
Guidelines
- [G1] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 10.1 Age-Related Macular Degeneration- Neovascular (n.d.). https://www.eyes.nhs.scot/eyecare-guidelines/section-10-retina/101-age-related-macular-degeneration-neovascular/