Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Ocular ultrasound and point-of-care ultrasound
Ocular ultrasound gives real-time images of the eye and orbit when the fundus cannot be seen or examination is limited [S3] [S12]. Point-of-care ultrasound (POCUS) by non-ophthalmologists is 94.2% sensitive and 96.3% specific for retinal detachment in a meta-analysis [S4], and handheld devices extend imaging to austere settings [S5]. It must be used with care in suspected open globe injury [S10].
Key points - Bedside ocular ultrasound is simple and quick and can help diagnose vitreous and retinal haemorrhage, retinal and vitreous detachment, infection, foreign bodies, retrobulbar haematoma and vascular pathology [S1]. - POCUS accuracy for retinal detachment did not differ significantly between emergency and non-emergency providers [S4]. - In suspected open globe injury, POCUS is highly sensitive and specific for some findings, but its use is controversial because of possible extrusion of globe contents [S10]. - Use the as-low-as-reasonably-achievable principle: the eye is one of the organs where exposure should be minimised [S7]. - Ultrasound biomicroscopy (UBM) is the only non-invasive high-resolution method for imaging the iridociliary complex and the anterior segment behind a corneal opacity [S8].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags: findings during the scan that need urgent action
- Suspected open globe (deep anterior chamber with retracted iris after trauma, haemorrhagic chemosis, hypotony, vitreous haemorrhage) [S2]. Stop, avoid any pressure on the eye, protect it and refer for surgical repair [S2] [S10].
- Retinal detachment on B-scan. Can cause significant vision loss if not rapidly diagnosed and referred [S4].
- Intraocular foreign body or retrobulbar haematoma [S1]: same-day ophthalmology.
- Enlarged optic nerve sheath diameter. A surrogate for raised intracranial pressure [S1] [S9]; urgent medical assessment [S1].
- Intraocular mass. Ultrasound measures posterior tumours and Doppler detects tumour vascularisation [S12]; refer to ocular oncology.
Recognise it: when to scan
- Opaque media or limited examination in the emergency setting [S1] [S3].
- Acute conditions readily diagnosed by ultrasound: retinal detachment, lens dislocation and globe rupture [S3].
- Occult globe rupture, when thorough slit-lamp examination is not possible (with CT) [S2].
- Children with corneal opacity or suspected anomalies behind the iris (UBM) [S8].
- Suspected raised intracranial pressure (optic nerve sheath diameter) [S1] [S9] [S11].
- Suspected giant cell arteritis: vascular ultrasound of the temporal arteries is a safe and reliable alternative to biopsy in rheumatology fast-track clinics, given an experienced sonographer [S6].
Confirm it: modes and technique
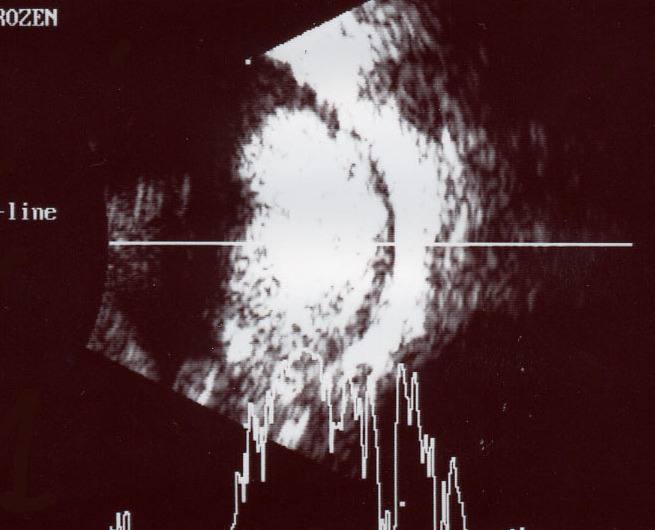
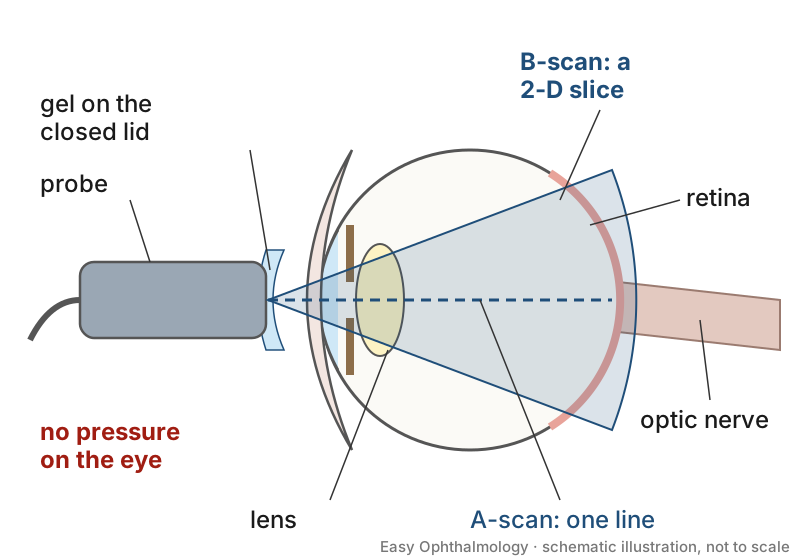
| Mode | Frequency | Main use [S12] |
|---|---|---|
| A-scan | 7 to 11 MHz | Tumour echogenicity (7 to 8 MHz), axial length (10 to 11 MHz) |
| B-scan | 10 to 20 MHz | Posterior segment, measuring posterior tumours |
| UBM | 40 to 100 MHz | Anterior segment structures |
| Doppler | n/a | Tumour and vessel blood flow |
- Emergency physicians can image anterior and posterior chamber structures with a linear probe [S3].
- A mnemonic-based systematic scan of the eye and surrounding structures has been proposed for emergency use [S1].
- Ultrasound penetrates further than OCT but has lower resolution, and needs an experienced operator for accurate probe positioning [S12].
- For optic nerve sheath measurement in children, combine standardised A-scan with B-scan for accurate, repeatable data [S11]; paediatric data are scarce [S11].
Manage it: doing and acting on the scan at each resource tier
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Where a portable ultrasound device and a trained user are available, it is a reliable, repeatable and inexpensive tool in austere settings [S5].
- Use it to look for retinal detachment and vitreous haemorrhage when the fundus cannot be seen [S1] [S4], then refer.
- Avoid scanning an eye with suspected open globe, because of the risk of extruding globe contents; protect it and refer [S10].
Tier B (general eye clinic)
- Use B-scan when opaque media or limited examination prevent a fundus view [S1] [S3].
- Train staff: safety begins with training in obtaining and interpreting valid images [S7].
- Keep output and exposure as low as possible [S7].
Tier C (specialist centre)
- Use A-scan, B-scan, UBM and Doppler for tumour characterisation and measurement [S12].
- Use UBM in children with corneal opacity and anterior segment anomalies [S8].
- Consider temporal artery ultrasound in suspected giant cell arteritis to speed diagnosis and avoid unnecessary steroid courses [S6].
Refer when
| Situation | Urgency |
|---|---|
| Suspected open or occult globe injury [S2] [S10] | Immediate |
| Retinal detachment on ultrasound [S4] | Same-day [EIC expert opinion] |
| Enlarged optic nerve sheath with headache or reduced consciousness [S9] | Medical emergency: follow your national protocol [EIC expert opinion] |
| Intraocular mass on ultrasound [S12] | Urgent to ocular oncology; timing per your local service or specialist advice |
Pitfalls
- Pressing on a possibly ruptured globe [S2] [S10].
- Assuming a normal CT excludes open globe injury [S10].
- Overestimating resolution: ultrasound cannot match OCT detail [S12].
- Relying on optic nerve sheath measurement in children, where data are scarce [S11].
- Long, high-output scanning of the eye [S7].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2014 | Narrative review |
| [S2] | 2018 | Narrative review |
| [S3] | 2019 | Narrative review |
| [S4] | 2019 | Systematic review and meta-analysis, 11 studies, 844 patients |
| [S5] | 2019 | Narrative review |
| [S6] | 2020 | Narrative review |
| [S7] | 2020 | Safety review |
| [S8] | 2021 | Systematic review |
| [S9] | 2021 | Narrative review |
| [S10] | 2023 | Narrative review |
| [S11] | 2023 | Narrative review |
| [S12] | 2023 | Narrative review |
- Only one source gives pooled accuracy data [S4]; most are narrative reviews, largely from emergency medicine.
- The meta-analysis found wide confidence intervals and called for work on training protocols [S4].
- Sources conflict on scanning in open globe injury: one reports high sensitivity, but also controversy over extrusion risk [S10].
- Not covered by these sources: accuracy for vitreous haemorrhage and intraocular foreign body, optic nerve sheath cut-off values, training hours needed, and device costs.
Related articles
- Rhegmatogenous Retinal Detachment
- Intraocular foreign body
- Uveal melanoma: diagnosis and primary treatment
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Kilker BA, Holst JM, Hoffmann B Bedside ocular ultrasound in the emergency department. European journal of emergency medicine : official journal of the European Society for Emergency Medicine. (2014). PubMed 24002686 · doi:10.1097/mej.0000000000000070
- [S2] Chronopoulos A, Ong JM, Thumann G, Schutz JS Occult globe rupture: diagnostic and treatment challenge. Survey of ophthalmology. (2018). PubMed 29649485 · doi:10.1016/j.survophthal.2018.04.001
- [S3] Tandon A, Khullar T, Bhatt S Sonography in acute ocular pathology: a kaleidoscopic view. Emergency radiology. (2019). PubMed 30446852 · doi:10.1007/s10140-018-1655-2
- [S4] Gottlieb M, Holladay D, Peksa GD Point-of-Care Ocular Ultrasound for the Diagnosis of Retinal Detachment: A Systematic Review and Meta-Analysis. Academic emergency medicine : official journal of the Society for Academic Emergency Medicine. (2019). PubMed 30636351 · doi:10.1111/acem.13682
- [S5] Canepa CA, Harris NS Ultrasound in Austere Environments. High altitude medicine & biology. (2019). PubMed 31112050 · doi:10.1089/ham.2018.0121
- [S6] Ching J, Smith SM, Dasgupta B, Damato EM The role of vascular ultrasound in managing giant cell arteritis in ophthalmology. Survey of ophthalmology. (2020). PubMed 31775013 · doi:10.1016/j.survophthal.2019.11.004
- [S7] Miller DL, Abo A, Abramowicz JS, Bigelow TA, Dalecki D, Dickman E, et al. Diagnostic Ultrasound Safety Review for Point-of-Care Ultrasound Practitioners. Journal of ultrasound in medicine : official journal of the American Institute of Ultrasound in Medicine. (2020). PubMed 31868252 · doi:10.1002/jum.15202
- [S8] Alexander JL, Wei L, Palmer J, Darras A, Levin MR, Berry JL, et al. A systematic review of ultrasound biomicroscopy use in pediatric ophthalmology. Eye (London, England). (2021). PubMed 32963311 · doi:10.1038/s41433-020-01184-4
- [S9] Yildizdas D, Aslan N Is Ocular Sonography a Reliable Method for the Assessment of Elevated Intracranial Pressure in Children? Journal of pediatric intensive care. (2021). PubMed 33585057 · doi:10.1055/s-0040-1716385
- [S10] Pelletier J, Koyfman A, Long B High risk and low prevalence diseases: Open globe injury. The American journal of emergency medicine. (2023). PubMed 36516669 · doi:10.1016/j.ajem.2022.11.036
- [S11] Abbinante G, Vitiello L, Coppola A, Salerno G, Gagliardi V, Pellegrino A Optic Nerve Ultrasound Evaluation in Children: A Review. Diagnostics (Basel, Switzerland). (2023). PubMed 36766639 · doi:10.3390/diagnostics13030535
- [S12] Kadakia A, Zhang J, Yao X, Zhou Q, Heiferman MJ Ultrasound in ocular oncology: Technical advances, clinical applications, and limitations. Experimental biology and medicine (Maywood, N.J.). (2023). PubMed 37212384 · doi:10.1177/15353702231169539