Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Pupil Abnormalities: Anisocoria and Horner Syndrome
Anisocoria indicates a problem of the efferent pupillary pathway; it can be harmless (physiological anisocoria) or the only sign of serious disease [S3]. Horner syndrome, from interruption of the oculosympathetic pathway, causes mild ptosis and a smaller pupil and may signal serious or life-threatening pathology in the head, neck or chest [S8]. Carotid artery dissection is the most common cause of isolated Horner syndrome found on imaging [S7].
Key points - Physiological anisocoria must be distinguished from Horner syndrome [S3]; pharmacological tests confirm Horner syndrome [S1] [S3]. - Painful, acute or traumatic Horner syndrome, or Horner syndrome with neurological signs, shapes the imaging work-up [S11]; carotid dissection is a cause of stroke and can present with pain and partial Horner syndrome [S5]. - In children, Horner syndrome of unknown cause may be the first sign of neuroblastoma or another mass and warrants imaging of brain, neck and thorax plus urinary catecholamines [S9]. - Tonic (Adie) pupils are mainly idiopathic and do not need imaging [S3], but infection, most commonly syphilis, is the main associated disease [S10]. - Disorders of the parasympathetic pathway include third nerve palsy and dorsal midbrain syndrome [S3].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Acute painful Horner syndrome (neck, occipital or head pain), or Horner syndrome after trauma or a recent procedure [S11]: think carotid dissection [S5] [S7].
- Horner syndrome with brain, cranial nerve or spinal cord signs [S11].
- Horner syndrome in a child without a known cause [S9].
- Large pupil with ptosis or eye movement limitation: third nerve palsy, a disorder of the parasympathetic pathway [S3]; see the cranial nerve palsies article.
- Bilateral light-near dissociation, the classic pupil sign of a dorsal midbrain lesion [S3].
Recognise it
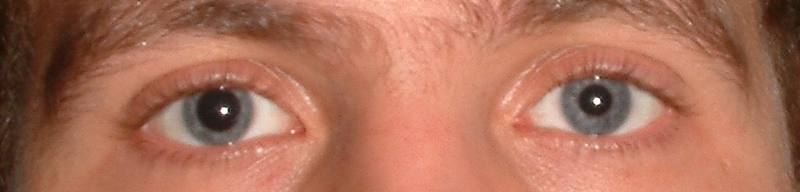
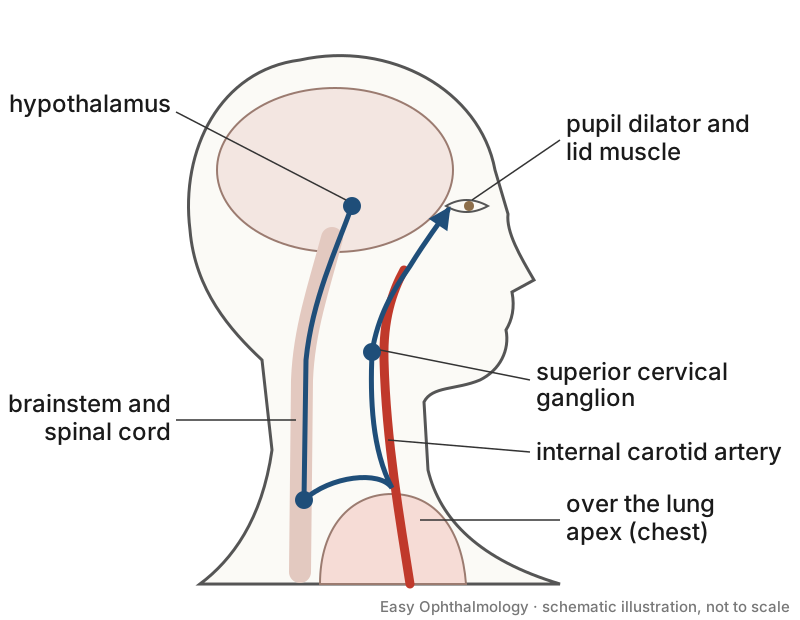
- Horner syndrome: the triad is ptosis, miosis and anhidrosis [S11], but patients rarely present with the full triad and often have no associated symptoms [S6]. Many cases are found incidentally at routine optometric assessment [S6]. Anhidrosis of the brow or face is less common [S8].
- The oculosympathetic pathway runs from the brain, down the spinal cord, out into the chest and back up the neck to the orbit, so the lesion can lie in the head, chest or neck [S8].
- Tonic (Adie) pupil: mainly in young women, usually unilateral; the affected pupil is larger, loses its light reaction and is sensitive to low-concentration pilocarpine [S10]. Differential diagnoses include third nerve palsy, anticholinergic drugs, Argyll Robertson pupil and congenital mydriasis [S10].
- Relative afferent pupillary defect indicates an afferent pathway disorder, not anisocoria [S3].
- Iris disease and cholinergic drugs can also impair the light reaction [S3].
Confirm it
- Pharmacological testing: cocaine testing, traditionally with hydroxyamphetamine for localisation; apraclonidine is a viable alternative, but false negatives and safety in young children are concerns [S1].
- Apraclonidine technique: in 14 healthy volunteers, apraclonidine 1% caused relative miosis in the normal eye, most marked at 30 to 60 minutes, so both eyes should receive drops when testing for Horner syndrome [S2]. Horner pupils dilate because of denervation supersensitivity [S2].
- These agents are rarely available during acute assessment or in general clinics, and localisation with hydroxyamphetamine needs about a week after cocaine or apraclonidine [S6]. A combined clinical and imaging protocol has been proposed for most settings [S6].
- Imaging yield: in 88 adults with isolated Horner syndrome imaged with MRI/MRA from the supraorbital ridge to T4, 20% had a cause, most commonly carotid dissection [S7].
- The ACR Appropriateness Criteria (2025) base imaging choice on onset (acute or not), pain, trauma and localising neurological signs [S11].
- In adults with clear evidence of chronic duration, imaging of isolated Horner syndrome may be deferred [S4].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- Check that the pupils are equal and react equally to light, and look for a droopy lid [S3] [S8].
- Refer new Horner syndrome with neck or head pain, trauma, or neurological symptoms urgently [S11] [S5].
- Refer any child with unexplained Horner syndrome [S9].
Tier B (general eye clinic)
- Separate efferent anisocoria from an afferent defect [S3].
- Confirm Horner syndrome with cocaine or apraclonidine if available, instilling both eyes [S1] [S2]; do not delay imaging in acute cases to perform drop tests [S6].
- Tonic pupil: no imaging needed in idiopathic cases [S3]; consider testing for syphilis, the most common associated disease, and immune or paraneoplastic disease [S10]. Low-dose pilocarpine helps confirm it, and pilocarpine can treat blurred vision [S10].
- In adults, imaging may be deferred only when chronic duration is clearly established [S4].
Tier C (specialist centre)
- Image according to the clinical scenario [S11]; MRI/MRA from the skull to T4 found a cause in 20% of isolated cases [S7].
- Children: cross-sectional imaging of brain, neck and thorax plus urinary catecholamines; in a systematic review, 17 of 152 children had a space-occupying lesion and 12 had neuroblastoma [S9].
- Carotid dissection: treatment options include antiplatelet or anticoagulant therapy and endovascular or surgical intervention; choice is controversial and no RCTs compare them [S5].
Refer when
| Situation | Urgency |
|---|---|
| Acute painful Horner syndrome, or after neck trauma or a procedure | Immediate, for vascular imaging [G2] [S5] [S11] |
| Dilated pupil with ptosis or diplopia | Immediate, as for third nerve palsy [G1] [S3] |
| Horner syndrome in a child without a known cause | Urgent, for imaging and urinary catecholamines; timing per your local service or specialist advice [S9] |
| Isolated tonic pupil or long-standing anisocoria | Routine; timing per your local service or specialist advice [S3] [S4] |
Pitfalls
- Expecting the full triad: it is rarely present [S6].
- Testing only the affected eye with apraclonidine [S2].
- Missing syphilis behind a tonic pupil [S10].
- Waiting a week for hydroxyamphetamine before imaging an acute case [S6].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2009 | Narrative review |
| [S2] | 2011 | Small experimental study, 14 healthy volunteers |
| [S3] | 2011 | Narrative review (textbook chapter) |
| [S4] | 2011 | Narrative review |
| [S5] | 2012 | Narrative review |
| [S6] | 2013 | Narrative review with proposed algorithm |
| [S7] | 2017 | Retrospective chart review, 88 patients |
| [S8] | 2018 | Narrative review |
| [S9] | 2019 | Systematic review of 8 retrospective studies, 152 children |
| [S10] | 2022 | Narrative literature review |
| [S11] | 2025 | ACR Appropriateness Criteria, expert panel |
- The evidence is mostly narrative review and small retrospective series; there are no trials of investigation strategies [S4] [S9].
- Conflict: imaging found a cause in 20% of isolated cases [S7], yet one review allows deferral in adults when chronicity is established [S4].
- The ACR abstract does not give its scenario-specific recommendations [S11].
- Not covered by these sources: the dilated pupil in third nerve palsy in detail, pharmacological mydriasis testing, and low-resource imaging alternatives.
Related articles
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Mughal M, Longmuir R Current pharmacologic testing for Horner syndrome. Current neurology and neuroscience reports. (2009). PubMed 19664368 · doi:10.1007/s11910-009-0056-z
- [S2] Cambron M, Maertens H, Crevits L Apraclonidine and my pupil. Clinical autonomic research : official journal of the Clinical Autonomic Research Society. (2011). PubMed 21384091 · doi:10.1007/s10286-011-0118-6
- [S3] Wilhelm H Disorders of the pupil. Handbook of clinical neurology. (2011). PubMed 21601076 · doi:10.1016/b978-0-444-52903-9.00022-4
- [S4] Al-Moosa A, Eggenberger E Neuroimaging yield in isolated Horner syndrome. Current opinion in ophthalmology. (2011). PubMed 21918445 · doi:10.1097/icu.0b013e32834bbf06
- [S5] Patel RR, Adam R, Maldjian C, Lincoln CM, Yuen A, Arneja A Cervical carotid artery dissection: current review of diagnosis and treatment. Cardiology in review. (2012). PubMed 22301716 · doi:10.1097/crd.0b013e318247cd15
- [S6] Davagnanam I, Fraser CL, Miszkiel K, Daniel CS, Plant GT Adult Horner's syndrome: a combined clinical, pharmacological, and imaging algorithm. Eye (London, England). (2013). PubMed 23370415 · doi:10.1038/eye.2012.281
- [S7] Beebe JD, Kardon RH, Thurtell MJ The Yield of Diagnostic Imaging in Patients with Isolated Horner Syndrome. Neurologic clinics. (2017). PubMed 27886891 · doi:10.1016/j.ncl.2016.08.005
- [S8] Martin TJ Horner Syndrome: A Clinical Review. ACS chemical neuroscience. (2018). PubMed 29260849 · doi:10.1021/acschemneuro.7b00405
- [S9] Braungart S, Craigie RJ, Farrelly P, Losty PD Paediatric Horner's syndrome: is investigation for underlying malignancy always required? Archives of disease in childhood. (2019). PubMed 31186293 · doi:10.1136/archdischild-2019-317007
- [S10] Xu SY, Song MM, Li L, Li CX Adie's Pupil: A Diagnostic Challenge for the Physician. Medical science monitor : international medical journal of experimental and clinical research. (2022). PubMed 35304432 · doi:10.12659/msm.934657
- [S11] Expert Panel on Neurological Imaging, Dubey P, Shekhrajka N, Juliano AF, Agarwal M, Antonio AA, et al. ACR Appropriateness Criteria® Horner Syndrome. Journal of the American College of Radiology : JACR. (2025). PubMed 41193044 · doi:10.1016/j.jacr.2025.08.041
Guidelines
- [G1] College of Optometrists (Guidance for Professional Practice). Annex 4 Urgency of referrals table (n.d.). https://www.college-optometrists.org/clinical-guidance/guidance/guidance-annexes/annex-4-urgency-of-referrals-table
- [G2] NHS Scotland (Community Eyecare Guidelines, eyes.nhs.scot). 1.9 Horner’s Syndrome (Oculosympathetic Palsy) (2026). https://www.eyes.nhs.scot/eyecare-guidelines/section-1-eyelids/19-horner-s-syndrome-oculosympathetic-palsy/