Educational content only. Not personalised medical advice. Clinical decisions remain the responsibility of the treating clinician.
Repeated low-level red-light therapy for myopia
Repeated low-level red-light (RLRL) therapy delivers 650-nm red light from a desktop device for 3 minutes, twice daily, to slow myopia progression in children [S1]. Trials report large short-term effects, but the 2025 Cochrane review rates the evidence as very low certainty [S9], and long-term retinal safety has not been established [S8] [S12].
Key points - In the first multicentre RCT (2022), RLRL reduced 12-month axial elongation by 0.26 mm and refractive progression by 0.59 D versus single-vision spectacles [S1]. - Cochrane (2025): RLRL may reduce 1-year progression by 0.80 D and axial elongation by 0.33 mm, but with very low-certainty evidence [S9]. - RLRL reduced myopia incidence in children with premyopia (40.8% vs 61.3% at 12 months) [S3]. - Rebound occurs after stopping, with faster axial elongation than in controls [S2] [S10]. - No permanent vision loss has been reported, but one child had a reversible fall in acuity with OCT changes; baseline and follow-up fundus imaging and OCT are advised [S8].
Evidence last checked: 2026-10-17 (PubMed abstracts).
Red flags
- Reduced vision, scotoma or prolonged afterimage during treatment. Stop the device and examine the retina. A reversible decline in visual acuity with OCT abnormalities was reported in one patient, resolving 4 months after stopping [S8]. The afterimage in reported studies resolved within 6 minutes [S8].
- Unsupervised use or devices of unknown power. Trials used class I devices of specified power under parental supervision [S1]; powers tested ranged from 0.29 mW to 1.20 mW [S1] [S4].
- Stopping without follow-up. Axial length rebounded after cessation [S2] [S10].
Recognise it: who was studied
- Children aged 8 to 13 years with -1.00 to -5.00 D [S1]; 6 to 12 years with -6 D to +3 D [S5]; 6 to 16 years with high myopia of at least -4.0 D [S6].
- Children with premyopia (-0.50 to +0.50 D and a myopic parent) in Shanghai primary schools [S3], and -0.50 to +0.75 D in a 2-year trial [S10].
- Nearly all trials were in China; a small RCT in Spain (26 children) studied RLRL with orthokeratology [S11].
Confirm it: before and during treatment
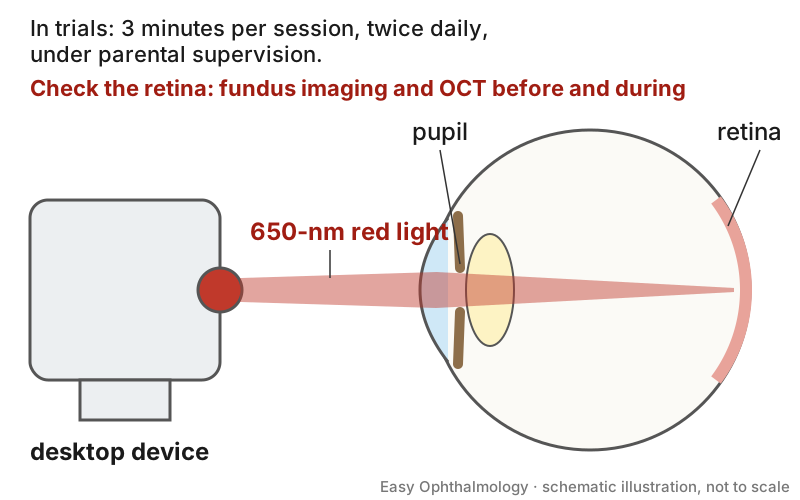
- Fundus photography and OCT before and during therapy, with home monitoring of visual acuity and afterimage duration, are recommended by a safety systematic review [S8].
- Efficacy trials measured cycloplegic refraction and axial length [S1] [S6].
Manage it
Before acting on this section, check the national and local guidelines, product information and regulatory approvals that apply where you practise. See the medical disclaimer.
Tier A (primary care / no specialist)
- RLRL is not a primary care treatment: it needs retinal imaging for safety monitoring [S8]. Correct the refractive error and refer for myopia assessment where available.
Tier B (general eye clinic)
- Discuss RLRL as an emerging option with very low-certainty evidence [S9].
Tier C (specialist centre)
- Regimen used in trials (as reported in [S1]): 650-nm light, about 1600 lux, 0.29 mW for a 4-mm pupil, 3 minutes per session, twice daily at least 4 hours apart, 5 days per week, at home under parental supervision. A 7-day regimen was used in high myopia [S6]; a meta-analysis found 5- and 7-day regimens comparable [S12]. Follow local device regulation; regimens are not a prescription.
- Expected effect. - Pooled 12-month effect versus control: +0.68 D and -0.30 mm, greater with higher baseline myopia; moderate certainty for refraction, lower certainty for axial length [S12]. - In high myopia, mean axial length changed by -0.06 mm with RLRL vs +0.34 mm with control; 53.3% had axial shortening of more than 0.05 mm [S6]. - Daily LLRL for 1 year: -0.11 mm vs +0.26 mm axial change [S5]. - Powers of 0.37, 0.60 and 1.20 mW were all effective over 6 months [S4].
- Prevention in premyopia. 12-month incidence 40.8% vs 61.3% (relative reduction 33.4%) [S3]. Over 2 years, axial elongation was 0.17 mm less than controls [S10].
- Continuing versus stopping. Children who continued RLRL in year 2 had 0.12 mm axial elongation; those who stopped had 0.42 mm, versus 0.28 mm in controls [S2]. After 1 year of cessation in premyopic children, axial elongation was faster than in controls [S10].
- Combination with orthokeratology. In Spanish children, RLRL plus ortho-K gave -0.124 mm axial change vs +0.102 mm with ortho-K alone at 12 months [S11].
- Safety monitoring. Side effect incidence was 0.088 per 100 patient-years; longer studies are needed [S8].
Refer when
| Situation | Urgency |
|---|---|
| Child on RLRL with reduced vision, central scotoma or afterimage lasting longer than usual | Same-day, with treatment stopped [EIC expert opinion] [S8] |
| Child or family requesting RLRL where no retinal imaging is available | Routine; timing per your local service or specialist advice |
| Rapid progression after stopping RLRL | Routine [S2]; timing per your local service or specialist advice |
Pitfalls
- Treating short-term axial shortening as proof of long-term benefit: trials are mostly 12 to 24 months [S8] [S12].
- Omitting retinal baseline imaging and follow-up [S8].
- Stopping abruptly without monitoring for rebound [S2] [S10].
- Generalising from Chinese trials: data from other populations are very limited [S11].
Evidence notes
| Source | Date | Design |
|---|---|---|
| [S1] | 2022 | Multicentre single-blind RCT, 264 children, China |
| [S2] | 2022 | Post-trial follow-up, 114 analysed |
| [S3] | 2023 | School-based RCT, premyopia, Shanghai |
| [S4] | 2024 | Single-centre RCT of 3 powers, 6 months |
| [S5] | 2024 | Single-masked RCT, 336 children, 1 site |
| [S6] | 2024 | Multicentre RCT, high myopia |
| [S7] | 2024 | Systematic review, 19 interventional studies |
| [S8] | 2024 | Safety systematic review, 20 studies |
| [S9] | 2025 | Cochrane living systematic review and NMA |
| [S10] | 2026 | RCT, premyopia, 2 years with washout |
| [S11] | 2026 | Non-blinded RCT, 26 children, Spain |
| [S12] | 2026 | Meta-analysis, 28 RCTs |
- Certainty conflicts between reviews: very low certainty for refraction in Cochrane [S9] vs moderate certainty in a 2026 meta-analysis [S12].
- Median study duration in the safety review was 9 months, longest 24 months [S8]; another review noted that more data are needed on safety [S7].
- The 2-year follow-up analysed only 57.3% of eligible children, with small subgroups [S2].
- The premyopia trial was disrupted by COVID-19 [S3].
- The authors of [S5] state that independent confirmation is needed.
- Not covered by these sources: device regulation, cost, long-term effects and effects on pathological myopia.
Related articles
- Low-dose atropine for myopia control
- Optical myopia control: spectacle lenses, contact lenses and orthokeratology
References
See the numbered source list below. Each marker [S#] links to its PubMed and DOI record.
Sources
- [S1] Jiang Y, Zhu Z, Tan X, Kong X, Zhong H, Zhang J, et al. Effect of Repeated Low-Level Red-Light Therapy for Myopia Control in Children: A Multicenter Randomized Controlled Trial. Ophthalmology. (2022). PubMed 34863776 · doi:10.1016/j.ophtha.2021.11.023
- [S2] Xiong R, Zhu Z, Jiang Y, Kong X, Zhang J, Wang W, et al. Sustained and rebound effect of repeated low-level red-light therapy on myopia control: A 2-year post-trial follow-up study. Clinical & experimental ophthalmology. (2022). PubMed 36054314 · doi:10.1111/ceo.14149
- [S3] He X, Wang J, Zhu Z, Xiang K, Zhang X, Zhang B, et al. Effect of Repeated Low-level Red Light on Myopia Prevention Among Children in China With Premyopia: A Randomized Clinical Trial. JAMA network open. (2023). PubMed 37099298 · doi:10.1001/jamanetworkopen.2023.9612
- [S4] Zhou W, Liao Y, Wang W, Sun Y, Li Q, Liu S, et al. Efficacy of Different Powers of Low-Level Red Light in Children for Myopia Control. Ophthalmology. (2024). PubMed 37634757 · doi:10.1016/j.ophtha.2023.08.020
- [S5] Cao K, Tian L, Ma DL, Zhao SQ, Li A, Jin ZB, et al. Daily Low-Level Red Light for Spherical Equivalent Error and Axial Length in Children With Myopia: A Randomized Clinical Trial. JAMA ophthalmology. (2024). PubMed 38662345 · doi:10.1001/jamaophthalmol.2024.0801
- [S6] Xu Y, Cui L, Kong M, Li Q, Feng X, Feng K, et al. Repeated Low-Level Red Light Therapy for Myopia Control in High Myopia Children and Adolescents: A Randomized Clinical Trial. Ophthalmology. (2024). PubMed 38849054 · doi:10.1016/j.ophtha.2024.05.023
- [S7] Chang DJ, P L S, Jeong J, Saw SM, Sevdalis N, Najjar RP Light Therapy for Myopia Prevention and Control: A Systematic Review on Effectiveness, Safety, and Implementation. Translational vision science & technology. (2024). PubMed 39167378 · doi:10.1167/tvst.13.8.31
- [S8] Chen Y, Xiong R, Yang S, Zhu Z, Li H, Xiang K, et al. Safety of repeated low-level red-light therapy for myopia: A systematic review. Asia-Pacific journal of ophthalmology (Philadelphia, Pa.). (2024). PubMed 39672511 · doi:10.1016/j.apjo.2024.100124
- [S9] Lawrenson JG, Huntjens B, Virgili G, Ng S, Dhakal R, Downie LE, et al. Interventions for myopia control in children: a living systematic review and network meta-analysis. The Cochrane database of systematic reviews. (2025). PubMed 39945354 · doi:10.1002/14651858.cd014758.pub3
- [S10] Liu G, Li N, Rong H, Hu J, Pei E, Pazo EE, et al. Two-year outcomes of repeated red light therapy in premyopic children: sustained efficacy and rebound effects. The British journal of ophthalmology. (2026). PubMed 41072941 · doi:10.1136/bjo-2025-327600
- [S11] Fernández Fidalgo MJ, Ferigo Ferrel VD, Wu Y, Qi Z, Yin-Moe Aung Y, Chen Y, et al. Repeated low-level red-light therapy combined with orthokeratology for myopia control in Spain: a randomised controlled study. The British journal of ophthalmology. (2026). PubMed 41266129 · doi:10.1136/bjo-2025-328347
- [S12] Lin LY, Hsu CH, Su H, Sun JW, Wu JS, Jeng WJ, et al. Duration-Dependent Efficacy and Clinical Safety of Repeated Low-Level Red-Light Therapy for Paediatric Myopia: A Systematic Review and Meta-Analysis. Clinical & experimental ophthalmology. (2026). PubMed 41846466 · doi:10.1111/ceo.70105